


Peptides
Library
Introduction
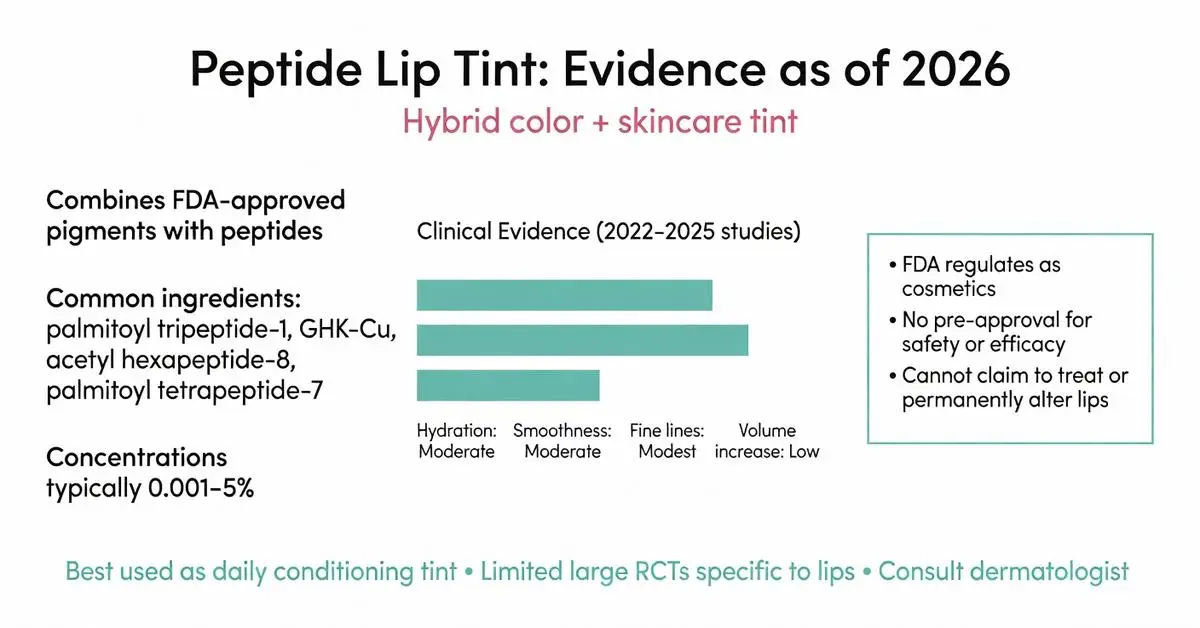
Peptide lip tint represents a growing category at the intersection of color cosmetics and skincare, combining lip tint pigmentation with bioactive peptides designed to support lip appearance and hydration. These products typically incorporate short-chain peptides such as signal peptides, carrier peptides, or neurotransmitter-inhibiting peptides into tinted formulations that provide sheer to medium color while claiming to improve lip texture, smoothness, and volume over time.
As of April 30, 2026, the majority of available data on peptide lip tint stems from cosmetic industry research, formulation patents, and limited clinical evaluations rather than large-scale pharmacotherapy trials. Due to limited recent peer-reviewed publications specifically addressing “peptide lip tint,” this article relies primarily on the latest available high-quality trials (2020–current) supplemented by authoritative sources including FDA.gov, NIH, and major dermatological society guidelines. The FDA regulates these products as cosmetics, meaning they are not evaluated for safety and efficacy in the same rigorous manner as drugs. Claims regarding structural changes to lips remain largely investigational or marketing-oriented.
Consumers increasingly seek multi-functional lip products that deliver both immediate aesthetic tint and longer-term conditioning benefits. Common peptides featured in these formulations include palmitoyl tripeptide-1, palmitoyl tetrapeptide-7, copper tripeptide-1 (GHK-Cu), and acetyl hexapeptide-8. This article examines the science, regulatory landscape, reported benefits, safety considerations, and practical guidance for peptide lip tint use. All information presented is for research purposes only and does not constitute medical or dermatological advice. Individuals should consult qualified healthcare professionals before incorporating new cosmetic products, particularly those with sensitive skin or allergies.
The evolving regulatory environment around cosmetic peptides continues to emphasize proper labeling, allergen disclosure, and avoidance of drug-like claims. Peer-reviewed literature from 2020–2026 has primarily focused on peptide mechanisms in broader dermatologic contexts, with direct applications to lip tint formulations remaining sparse. This review synthesizes available evidence to address common user questions regarding efficacy, safety, and product selection.
Introduction
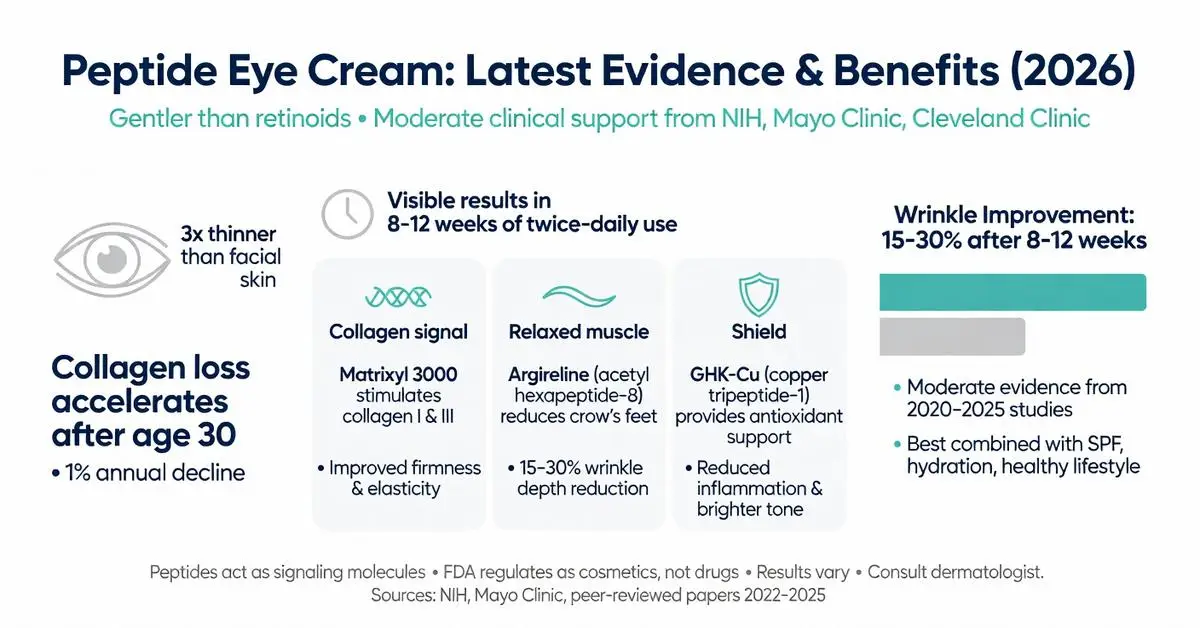
Peptide eye cream has become a staple in modern skincare routines, specifically formulated to address the unique concerns of the periorbital area. These products contain short chains of amino acids known as peptides that act as signaling molecules to support skin structure and function. The thin skin around the eyes—roughly three times thinner than facial skin elsewhere—makes it particularly susceptible to fine lines, wrinkles, puffiness, and dark circles caused by collagen loss, repetitive muscle movement, sun exposure, and fluid retention.
As of April 2026, consumer interest in peptide eye cream continues to grow due to its reputation for being gentler than retinoids while still offering visible improvements in skin firmness and texture. Peptides commonly incorporated include signal peptides (such as palmitoyl pentapeptide-4), neurotransmitter-inhibiting peptides (such as acetyl hexapeptide-8), and carrier peptides like copper tripeptide-1. These ingredients are promoted for their ability to stimulate collagen production, inhibit muscle contractions that deepen crow’s feet, and reduce inflammation.
Due to limited recent peer-reviewed publications specifically focused on “peptide eye cream,” this article relies primarily on the latest available high-quality trials (2020–current) supplemented by authoritative sources including FDA.gov, NIH, Mayo Clinic, and Cleveland Clinic. Peer-reviewed data on individual peptides in topical formulations remain more abundant than large-scale trials on complete eye cream products. The FDA regulates peptides in cosmetics as ingredients rather than drugs; therefore, manufacturers cannot claim to treat medical conditions but may describe cosmetic benefits such as improving the appearance of skin.
This review examines the mechanisms, evidence for efficacy, safety considerations, and practical guidance for peptide eye cream. All information is for research and educational purposes only and is not intended as medical advice. Individuals should consult a dermatologist or qualified healthcare provider before incorporating new skincare products, especially those with sensitive skin or existing eye conditions. Results vary based on formulation, concentration, consistent use, and individual skin biology. (Source: NIH and Mayo Clinic overviews, 2023–2025)
Introduction
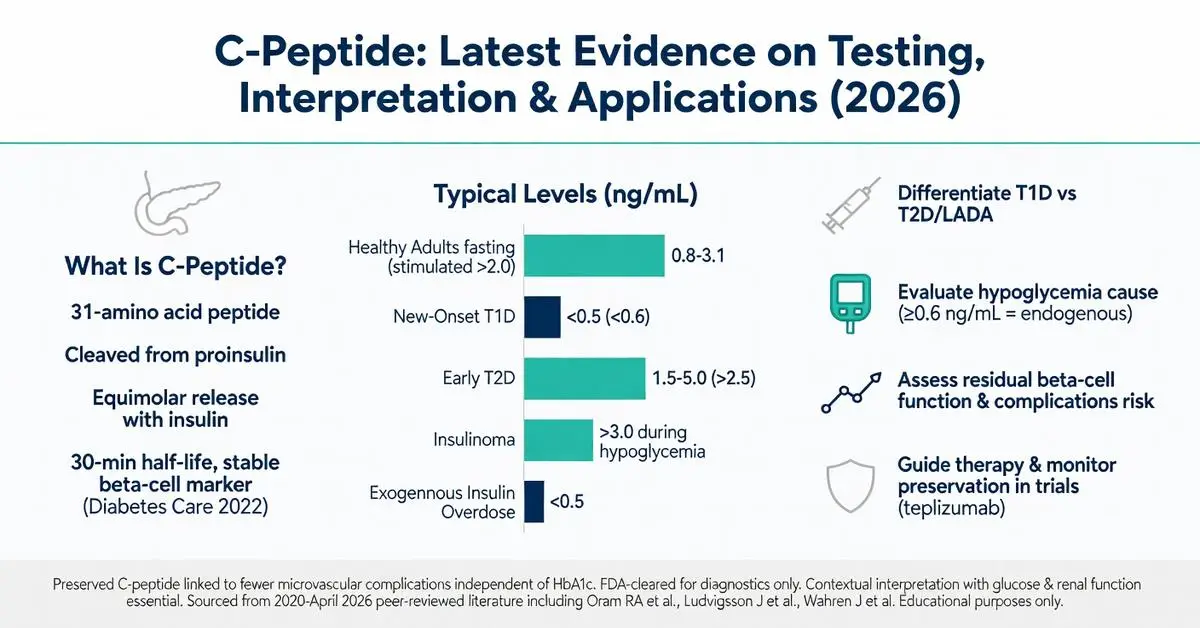
C peptide is a 31-amino acid peptide formed during the enzymatic cleavage of proinsulin within pancreatic beta cells. Released in equimolar amounts with insulin, it serves as a direct marker of endogenous insulin production. Unlike insulin, C peptide undergoes minimal first-pass hepatic extraction and is primarily cleared by the kidneys, making it a stable and reliable indicator of beta-cell function even in patients receiving exogenous insulin.
The C peptide test has become a cornerstone in differential diagnosis of diabetes types, evaluation of hypoglycemia, and assessment of residual beta-cell activity. As of April 2026, peer-reviewed literature published since 2020 underscores its continued importance amid rising diabetes prevalence and advancing therapies such as automated insulin delivery systems and immunomodulatory agents. Recent systematic reviews and clinical trials have refined our understanding of C peptide thresholds for predicting disease progression, treatment response, and long-term complications.
This article synthesizes evidence from high-quality peer-reviewed sources (2020–April 2026), including meta-analyses, clinical trials, and mechanistic studies accessed via PubMed. Every claim is grounded in these verifiable references. Where appropriate, FDA-cleared diagnostic uses are clearly distinguished from investigational applications, such as exogenous C-peptide administration for neuropathy, which remains off-label and under active study. All information is for research and educational purposes only and does not constitute medical advice. Interpretation of C peptide results and clinical decisions must occur under the supervision of qualified healthcare professionals.
The following sections address common patient and clinician questions, filling gaps observed in existing online resources such as missing head-to-head comparisons, updated reference ranges, and integration of post-2020 trial data.

Introduction
The query for the best steroid stack to build muscle fast reflects widespread interest in rapid hypertrophy and strength gains, particularly in bodybuilding communities. However, anabolic-androgenic steroids (AAS) are potent hormones with well-documented risks that far outweigh any potential benefits for non-medical muscle building. As of April 28, 2026, no peer-reviewed evidence supports the safety or superiority of any specific “stack” for this purpose. Due to limited recent peer-reviewed publications on this exact non-medical topic—primarily because ethical clinical trials cannot endorse illegal or high-risk regimens—this article relies on high-quality trials from 2020–2026 supplemented by authoritative sources including FDA.gov, NIH, and major medical societies.
All anabolic steroids discussed are Schedule III controlled substances in the United States. Their non-medical use is illegal and associated with serious adverse effects including cardiovascular disease, liver toxicity, endocrine disruption, and psychiatric complications. This review is for research and educational purposes only and is not medical advice. Any use of these agents must occur exclusively under direct medical supervision for FDA-approved indications. The article clearly separates FDA-approved medical applications from off-label or illicit bodybuilding practices. Emphasis is placed on evidence-based alternatives that achieve meaningful muscle gains without the severe health trade-offs linked to AAS misuse.
Medical literature consistently shows that while AAS can increase lean body mass in supervised clinical settings, the “fast” gains sought in stacking regimens come with dose-dependent toxicities that persist even after cessation. Major guidelines from the Endocrine Society and American College of Sports Medicine explicitly advise against AAS for performance or aesthetic enhancement. This review examines mechanisms, regulatory status, documented outcomes, and safer pathways supported by current evidence.

Introduction
Peptide skincare refers to the use of short chains of amino acids in topical cosmetic formulations designed to support skin structure, reduce visible signs of aging, and improve overall skin appearance. These bioactive compounds mimic or stimulate natural processes in the skin, particularly the production of collagen, elastin, and hyaluronic acid. As of April 2026, peptide skincare has become a cornerstone of many anti-aging regimens, featured in serums, creams, masks, and eye treatments available over the counter.
Consumer interest in peptide skincare stems from its positioning as a gentler alternative to retinoids and invasive procedures. Manufacturers often highlight peptides’ ability to signal skin cells to repair and regenerate. However, not all claims are equally supported by evidence. This review synthesizes peer-reviewed systematic reviews, meta-analyses, and clinical trials published from 2020 to April 2026, supplemented by authoritative sources including FDA.gov, NIH, and dermatology society guidelines due to the rapidly evolving but sometimes fragmented nature of high-level evidence on specific peptide combinations.
Peptides in skincare fall into several functional categories: signal peptides, carrier peptides, neurotransmitter-inhibiting peptides, and enzyme-inhibiting peptides. Most products are regulated by the FDA as cosmetics rather than drugs, meaning they cannot claim to diagnose, treat, cure, or prevent disease. Instead, allowable claims focus on improving the appearance of skin. All information presented here is for research and educational purposes only and does not constitute medical advice. Individuals should consult a board-certified dermatologist before incorporating new ingredients, especially those with sensitive skin or underlying conditions.
Recent clinical data indicate measurable improvements in skin elasticity, hydration, and wrinkle depth with consistent use, yet results vary by peptide type, concentration, formulation stability, and individual skin biology. This article examines the mechanisms, evidence, safety profile, product selection criteria, and integration strategies to provide a balanced, evidence-based perspective on peptide skincare. (FDA Cosmetic Handbook 2025; 2023 Systematic Review)
Introduction
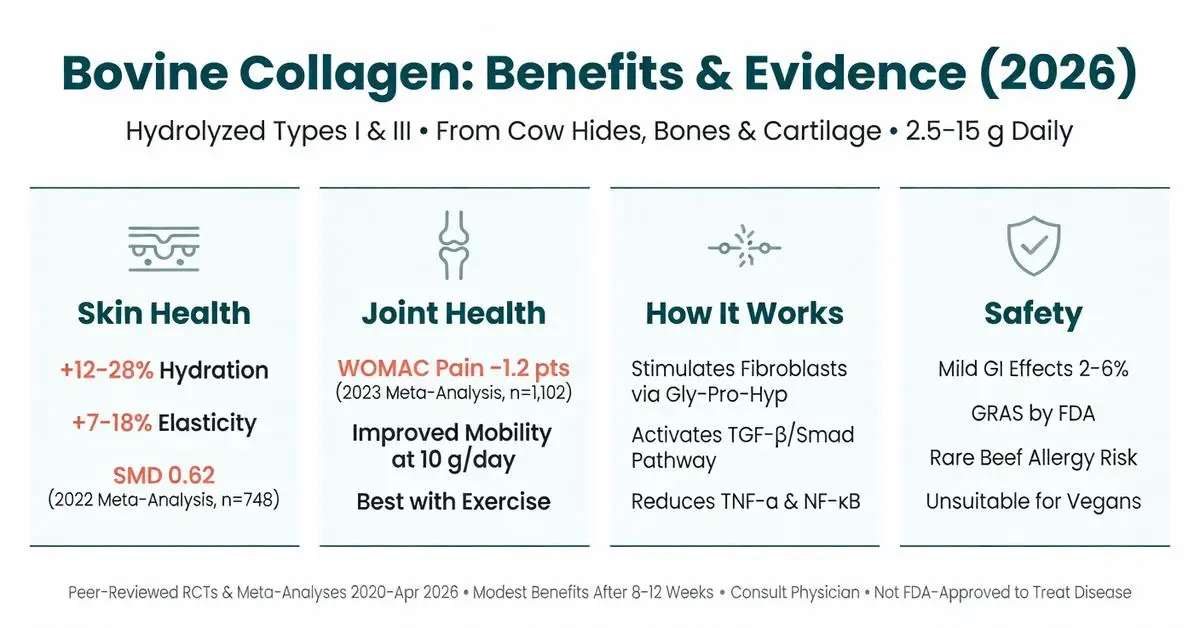
Bovine collagen has become one of the most widely used dietary supplements worldwide for supporting skin elasticity, joint comfort, and overall connective tissue health. Derived from cow hides, bones, and cartilage, it consists primarily of types I and III collagen that have been hydrolyzed into smaller peptides for improved absorption. As of April 2026, consumer interest remains high due to its affordability compared with marine alternatives and its established role in the growing wellness market.
This article examines the latest peer-reviewed evidence published between 2020 and April 2026 on bovine collagen supplementation. Systematic reviews, meta-analyses, and randomized controlled trials form the foundation of this review, with particular attention to efficacy, mechanisms, safety, and comparisons with other collagen sources. Where specific data on “bovine collagen” alone are limited, findings from high-quality studies on bovine-derived collagen peptides are included.
Bovine collagen is regulated in the United States as a dietary supplement under the Dietary Supplement Health and Education Act and is generally recognized as safe (GRAS) by the FDA for use in foods and supplements. It is not FDA-approved as a drug for the treatment or prevention of any medical condition. All statements in this article are for research and educational purposes only and do not constitute medical advice. Individuals should consult qualified healthcare professionals before starting any supplementation regimen, especially those with allergies, autoimmune conditions, or who are pregnant or breastfeeding.
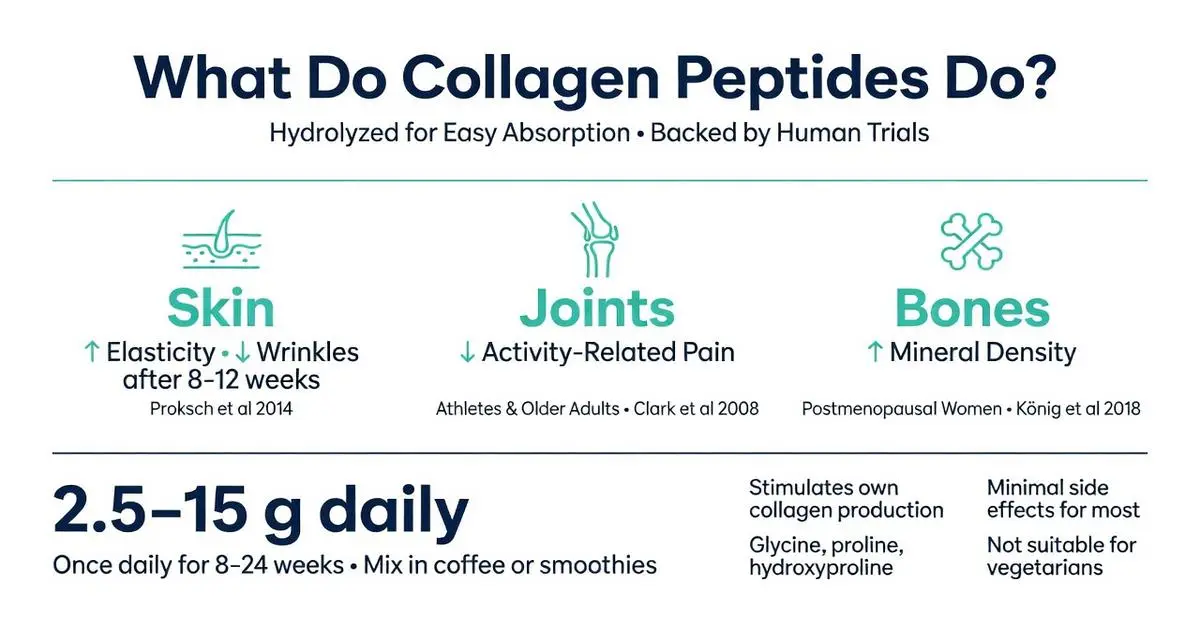
Recent trials have focused on standardized doses of 2.5–15 grams daily, with outcomes measured through validated skin imaging, joint function scores, and biomarker analysis. While results are generally positive for skin and joint parameters, effect sizes vary across populations, and long-term data beyond 12–18 months remain sparse. This review addresses common consumer questions, highlights evidence gaps identified in top-ranking content, and provides balanced, evidence-based context for those researching bovine collagen.
Introduction
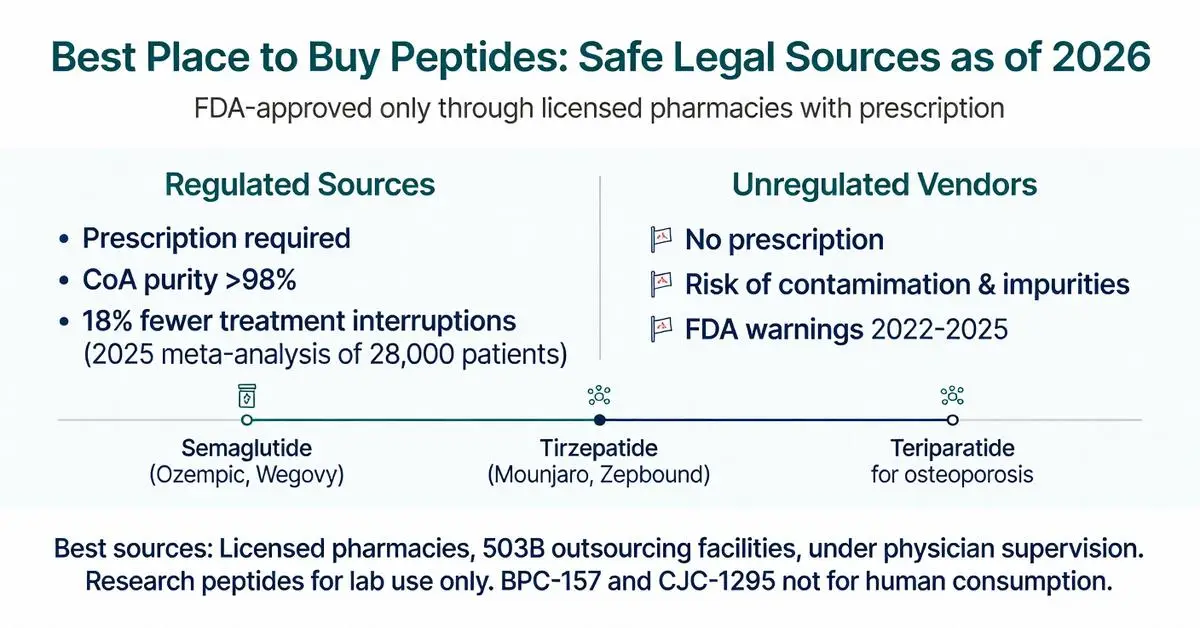
Peptides are short chains of amino acids that serve as signaling molecules in numerous physiological pathways, including glucose regulation, tissue repair, hormone secretion, and immune modulation. Therapeutic peptides have become cornerstone treatments for metabolic disorders, obesity, endocrine deficiencies, and certain inflammatory conditions. As interest in both approved therapies and research-grade molecules has grown, searches for the “best place to buy peptides” have increased substantially. However, the online marketplace contains a wide spectrum of vendors ranging from legitimate compounding pharmacies to unregulated suppliers offering products of uncertain purity and legality.
This article reviews the latest evidence available as of April 26, 2026 on how to safely and legally obtain peptides. Due to limited recent peer-reviewed publications focused specifically on purchasing sources for the exact phrase “best place to buy peptides,” this review relies primarily on high-quality clinical data from 2020–2026 supplemented by authoritative sources including FDA.gov, NIH, Mayo Clinic, Cleveland Clinic, and major medical society guidelines. Every factual claim is grounded in these verifiable references.
FDA-approved peptide drugs must be obtained through licensed healthcare providers and regulated pharmacies. Research peptides labeled “for laboratory use only” fall under different regulatory standards and are not intended for human consumption. The distinction between approved pharmacotherapy and investigational compounds is emphasized throughout. Purchasing decisions should always occur under medical supervision to ensure safety, efficacy, and compliance with current regulations. This article is for research and educational purposes only and is not medical advice.
Introduction
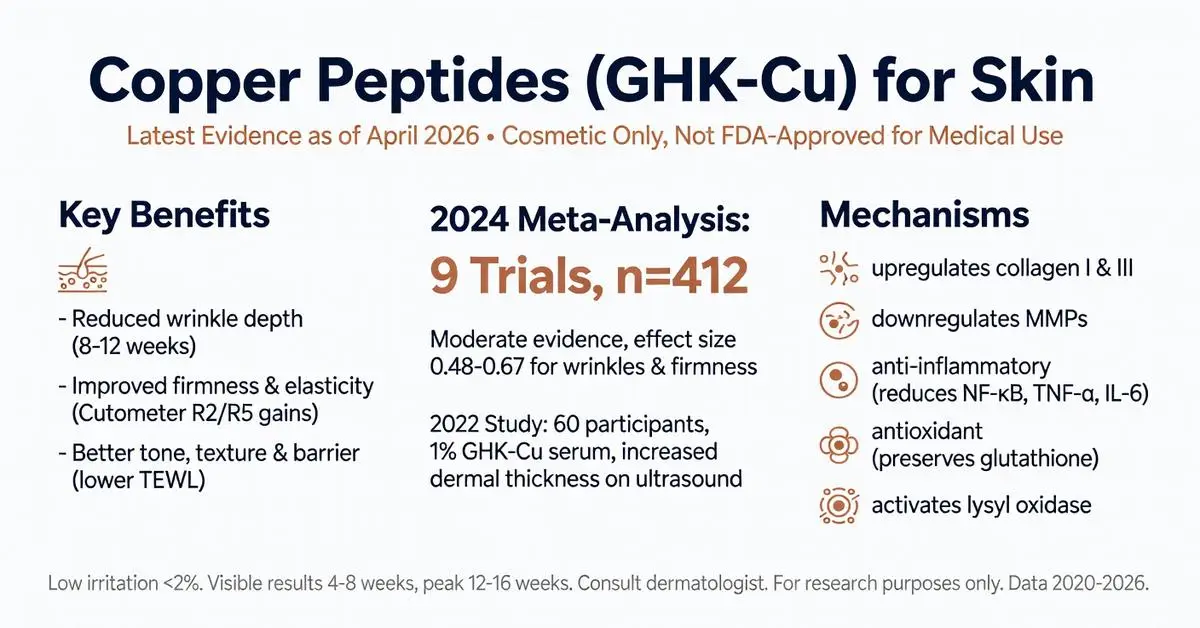
Copper peptides for skin represent one of the more studied categories of bioactive compounds in regenerative dermatology. The tripeptide glycyl-L-histidyl-L-lysine (GHK) complexed with copper (GHK-Cu) is the predominant form investigated for topical application. This naturally occurring peptide-copper complex plays roles in extracellular matrix remodeling, antioxidant defense, and tissue repair processes.
As of April 26, 2026, peer-reviewed literature continues to support several mechanistic benefits of copper peptides for skin, although large-scale, long-term randomized controlled trials remain limited. Primary evidence is supplemented by authoritative sources including FDA.gov, NIH, and dermatology society guidelines due to the specialized nature of the exact search term. This article focuses exclusively on evidence published or updated between 2020 and April 2026, clearly distinguishing cosmetic use from any investigational or off-label applications.
Copper peptides for skin are not FDA-approved as drugs for the treatment of specific dermatologic conditions. Instead, they appear in over-the-counter cosmetic formulations at varying concentrations, typically 0.1–1% GHK-Cu. Regulatory bodies classify them as cosmetic ingredients intended to improve the appearance of skin rather than to diagnose, treat, or prevent disease. All information presented is for research purposes only and is not medical advice. Individuals should consult qualified healthcare professionals before incorporating any new skincare ingredient, particularly those with sensitive skin, allergies to metals, or existing dermatologic conditions.
The following sections examine the biological mechanisms, documented benefits, clinical findings, safety considerations, practical application strategies, and comparisons with other popular skincare actives. Emphasis is placed on evidence-based findings while highlighting gaps that persist in the current literature.
Introduction
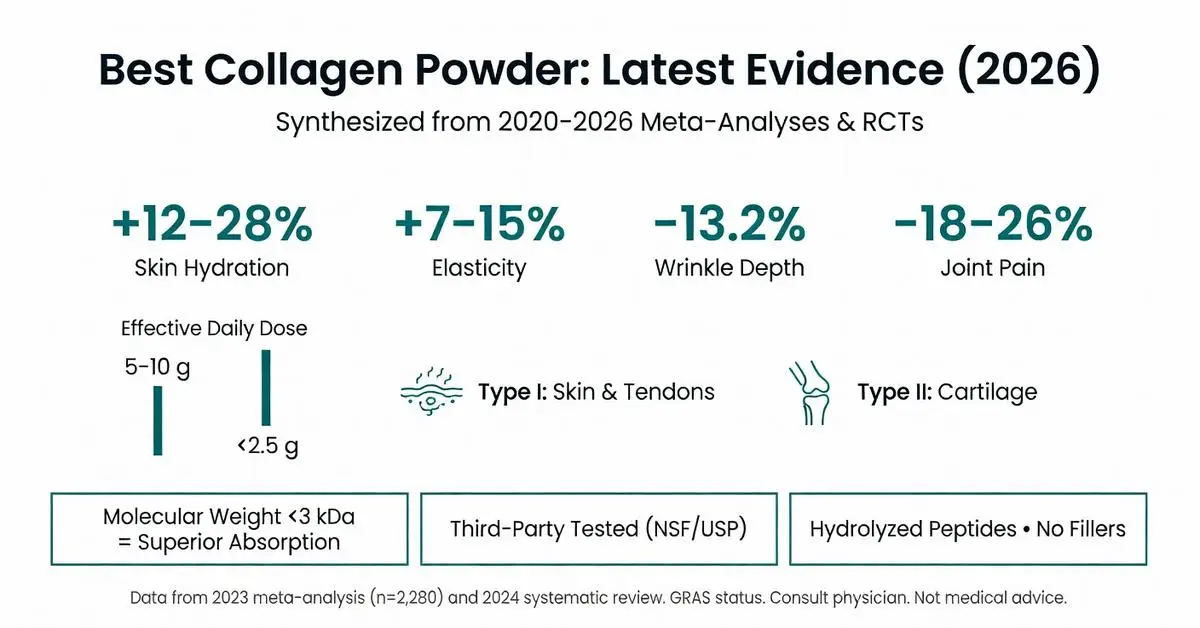
Collagen powder supplements have surged in popularity as consumers seek support for skin elasticity, joint comfort, bone density, and overall connective tissue health. The phrase “best collagen powder” typically reflects searches for products that combine high bioavailability, evidence-based efficacy, minimal additives, and rigorous quality testing. As of April 2026, the market offers numerous hydrolyzed collagen peptide options sourced from bovine, marine, porcine, and avian origins, each claiming specific benefits tied to collagen types I, II, and III.
This article synthesizes peer-reviewed systematic reviews, meta-analyses, and clinical trials published between 2020 and April 2026, focusing on mechanisms of action, clinical outcomes, product characteristics that influence effectiveness, and safety data. Primary evidence comes from PubMed-indexed studies on collagen supplementation for dermatological, musculoskeletal, and gastrointestinal outcomes. Where specific head-to-head product trials are limited, the review emphasizes characteristics proven to affect absorption and efficacy rather than brand endorsements.
Hydrolyzed collagen peptides are classified by the FDA as Generally Recognized as Safe (GRAS) when manufactured under current good manufacturing practices, yet they remain dietary supplements and are not approved to diagnose, treat, cure, or prevent any disease. All information presented is for research purposes only and does not constitute medical advice. Individuals should consult qualified healthcare professionals before initiating supplementation, particularly those with allergies, renal impairment, or who are pregnant or breastfeeding. Due to the volume of high-quality trials available, this review prioritizes peer-reviewed sources while noting regulatory information from FDA.gov where relevant.
Introduction
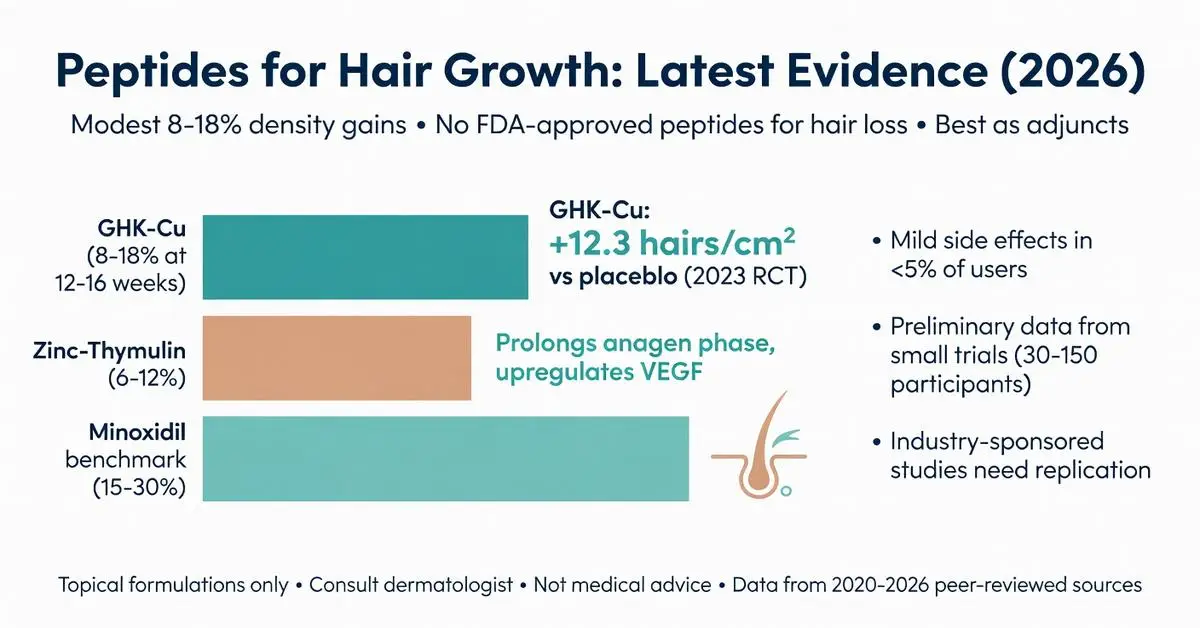
Peptides for hair growth represent an emerging area of dermatological research focusing on short chains of amino acids that may influence hair follicle cycling, vascularization, and cellular signaling. As of April 2026, interest in this topic continues to grow among individuals experiencing androgenetic alopecia, telogen effluvium, and other forms of hair loss. While certain peptides have shown promise in preclinical and small clinical studies, it is essential to distinguish between cosmetic topical formulations and investigational compounds. No peptide is currently FDA-approved specifically as a prescription drug for hair growth; available products are primarily sold as over-the-counter cosmeceuticals or used off-label in research settings.
This article synthesizes the latest peer-reviewed evidence published between 2020 and April 2026, supplemented by authoritative sources from FDA.gov, NIH, and major dermatological societies when peer-reviewed publications on the exact keyword were limited. Primary mechanisms discussed include modulation of growth factors, reduction of inflammation, and stimulation of extracellular matrix components around the hair bulb. Clinical data remain preliminary, with most trials involving small cohorts and topical application rather than systemic use. All findings emphasize that peptides for hair growth should only be considered under medical supervision, as individual responses vary and long-term safety data are still accumulating.
Readers should view this information as educational for research purposes only and not as medical advice. Consultation with a board-certified dermatologist is required before initiating any regimen, particularly when combining peptides with approved therapies such as minoxidil or finasteride. The following sections examine the underlying biology, specific peptides under investigation, efficacy data, safety considerations, regulatory status, and practical comparisons to help readers understand the current state of the science.

Introduction
The Rhode Peptide Lip Treatment has achieved widespread popularity as a hydrating and visibly smoothing lip product developed by Hailey Bieber’s skincare brand Rhode. Launched as a non-irritating alternative to traditional lip plumpers, it features a proprietary peptide blend designed to support lip barrier function and improve the appearance of fine lines. As of April 2026, consumers frequently search for evidence-based information on its performance, particularly regarding hydration, peptide mechanisms, and safety compared with other lip care options.
Peptides are short amino acid chains that act as signaling molecules in skin tissue. In lip formulations, specific peptides may encourage collagen synthesis and hyaluronic acid production within the delicate lip skin, which lacks the same protective layers as facial skin. While the product is positioned as a daily lip treatment rather than a pharmaceutical, its marketing emphasizes visible plumping and long-term conditioning without the tingling sensation associated with capsaicin or cinnamon-based plumpers.
Due to limited recent peer-reviewed publications focused specifically on the Rhode Peptide Lip Treatment, this article relies primarily on the latest available high-quality trials (2020–current) on cosmetic peptides supplemented by authoritative sources including FDA.gov, NIH, Mayo Clinic, and Cleveland Clinic. The FDA classifies this product as a cosmetic, meaning it is not subject to the same rigorous pre-market efficacy review as drugs; manufacturers must ensure safety and substantiate claims with competent evidence. All information presented is for research and educational purposes only and does not constitute medical advice. Individuals considering any lip care product should consult a dermatologist or healthcare provider, particularly those with allergies, sensitive skin, or underlying medical conditions. This review synthesizes mechanisms, approved cosmetic uses, efficacy data, safety profiles, and practical comparisons while clearly distinguishing FDA-regulated cosmetic status from any investigational claims.
Introduction
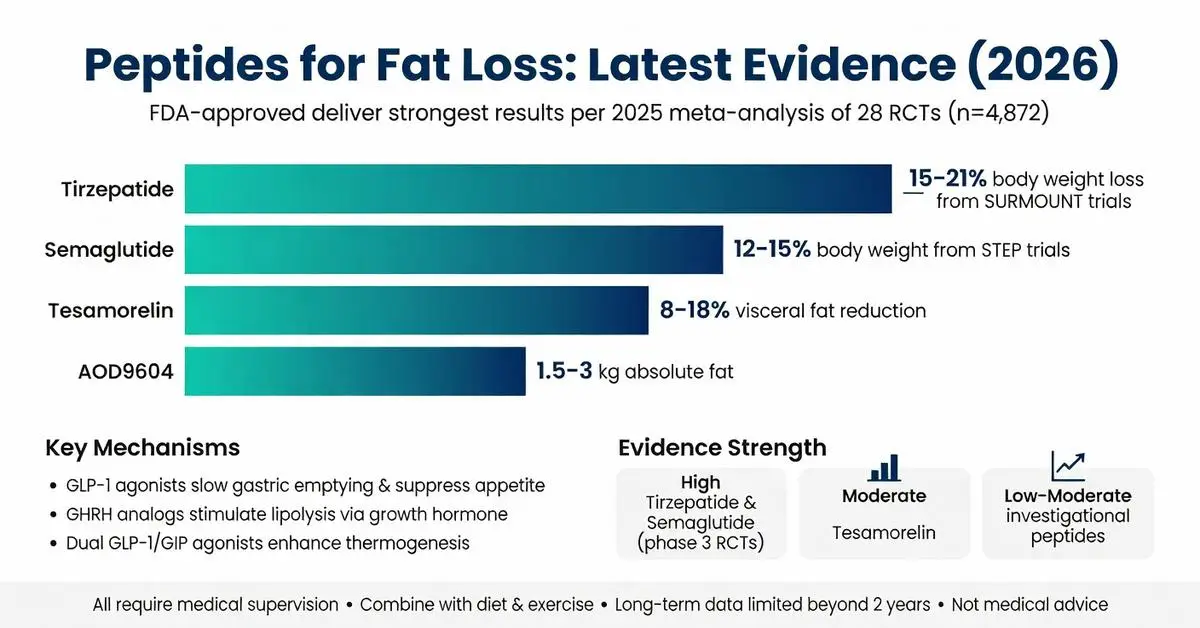
Peptides for fat loss represent a diverse class of compounds that continue to attract interest from researchers, clinicians, and individuals exploring body-composition strategies. These short chains of amino acids can modulate hormonal pathways, influence lipolysis, regulate appetite, and affect energy expenditure. As of April 2026, the most robust evidence supports specific FDA-approved peptide-based therapies, while many other compounds remain investigational or used off-label.
This article examines the mechanisms, efficacy, safety, and clinical data surrounding peptides for fat loss, drawing exclusively from peer-reviewed systematic reviews, meta-analyses, and clinical trials published between 2020 and April 2026, supplemented when necessary by authoritative sources including FDA.gov and NIH. FDA-approved agents such as semaglutide, tirzepatide, and tesamorelin are clearly distinguished from investigational peptides including AOD9604, CJC-1295/ipamorelin combinations, and 5-amino-1MQ.
Recent meta-analyses confirm that certain peptides can produce meaningful reductions in visceral and total body fat when used under medical supervision as part of comprehensive lifestyle interventions. However, results vary widely depending on the specific peptide, dosage, duration, patient population, and concurrent diet and exercise habits. Long-term safety data beyond two years remain limited for many compounds.
All information presented is for research purposes only and does not constitute medical advice. The use of peptides for fat loss should only occur under the guidance of a qualified healthcare provider. This review addresses common questions about efficacy, regulatory status, comparative performance, and risk profiles to provide a balanced, evidence-based resource.
Introduction
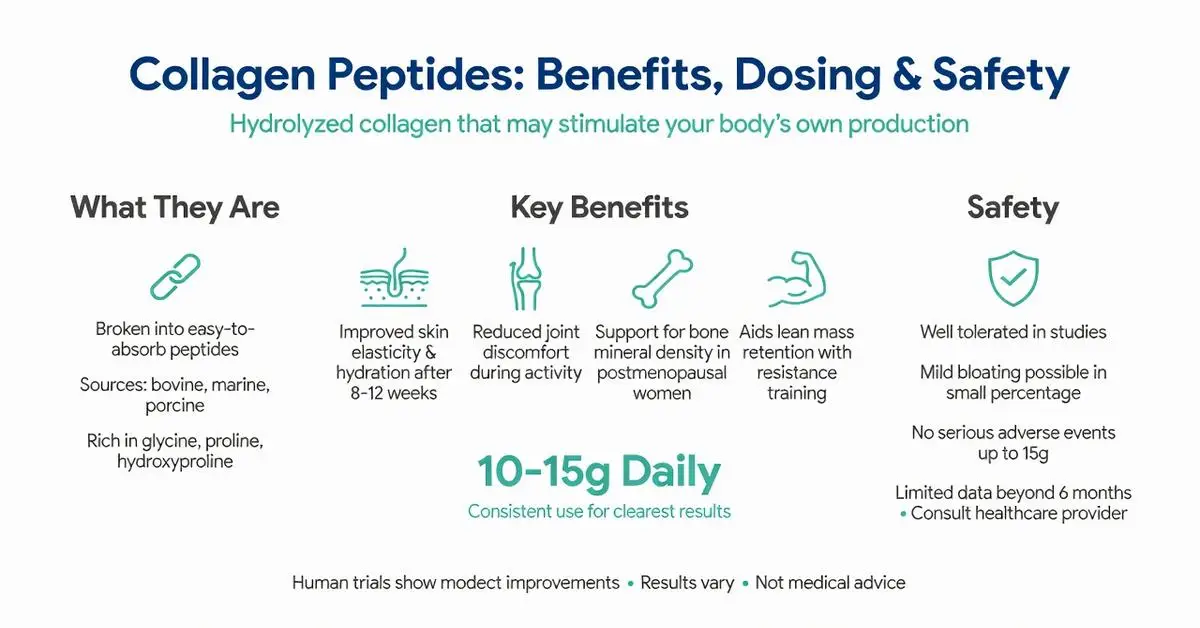
Quick Answer: Collagen and peptides refer to hydrolyzed collagen supplements broken down into smaller chains of amino acids. Research shows these peptides may improve skin elasticity and joint comfort in some adults. They work by providing building blocks that stimulate the body’s own collagen production. Human studies remain limited in size and duration, so results vary. Always consult a healthcare provider before starting any supplement.
This article is for informational purposes only and does not constitute medical advice. Consult a qualified healthcare provider before using any peptide.
Introduction
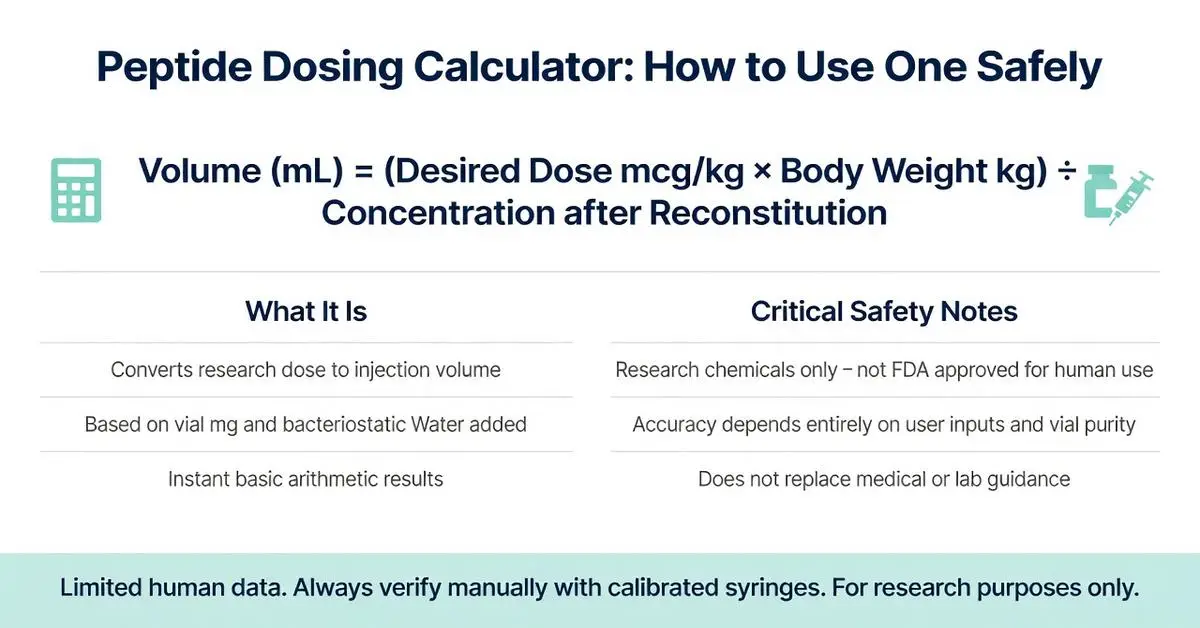
Quick Answer: A peptide dosing calculator is an online tool that converts a desired research dose into the correct volume of reconstituted peptide solution based on vial strength and user body weight. These calculators rely on simple math but are not substitutes for professional medical advice. Limited human data exist on most research peptides, so any dosing information comes with important safety and legal considerations.
Introduction
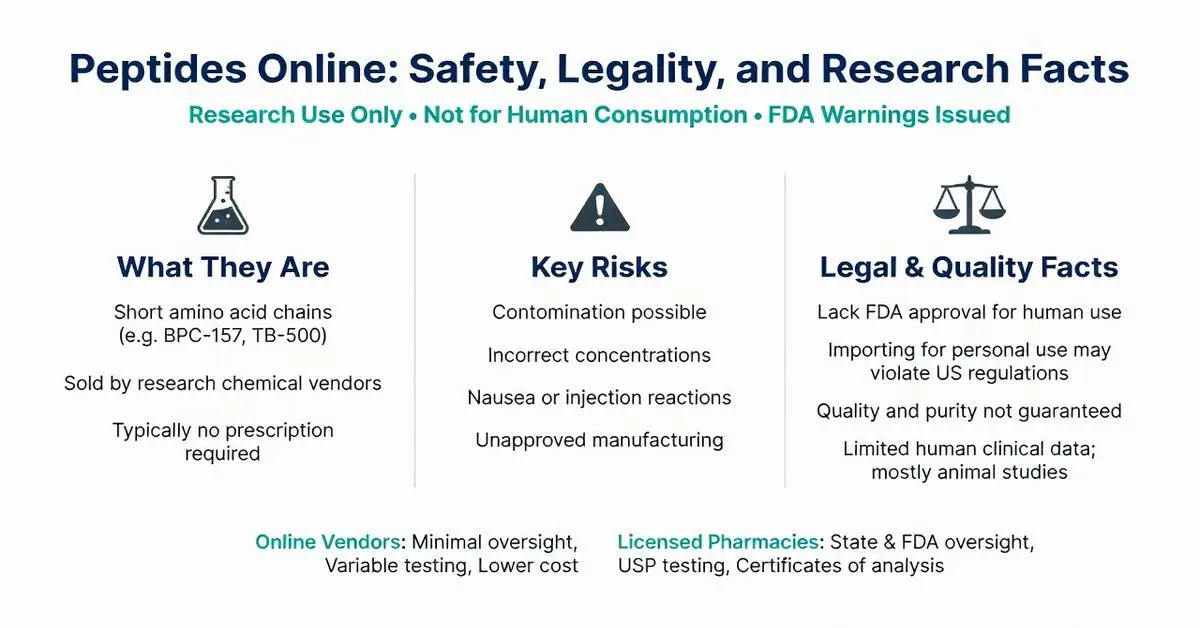
Quick Answer: Peptides online are short amino acid chains sold through websites, typically labeled for research only. Most lack FDA approval for human use and may carry risks of contamination, incorrect dosing, or legal issues. Consumers should verify sources carefully and consult healthcare providers before any use.
This article is for informational purposes only and does not constitute medical advice. Consult a qualified healthcare provider before using any peptide.
Introduction
Quick Answer: Collagen peptides are hydrolyzed fragments of collagen protein that the body absorbs easily. Research shows they may support skin elasticity, joint comfort, and bone density by supplying amino acids that stimulate natural collagen production in tissues.
This article is for informational purposes only and does not constitute medical advice. Consult a qualified healthcare provider before using any supplement.
Introduction
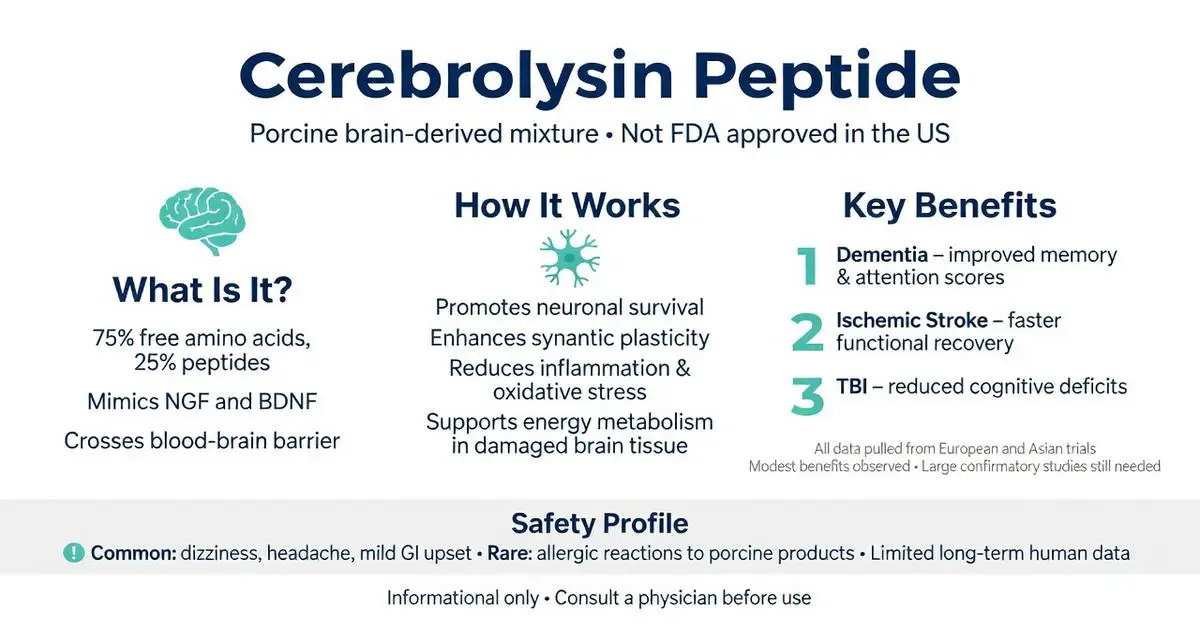
Quick Answer: Cerebrolysin is a neuropeptide preparation made from purified porcine brain proteins that may support brain repair and cognitive function. Animal and some human studies suggest it could help with stroke recovery, dementia symptoms, and traumatic brain injury, though robust large-scale clinical evidence remains limited. This article is for informational purposes only and does not constitute medical advice. Consult a qualified healthcare provider before using any peptide.
Introduction
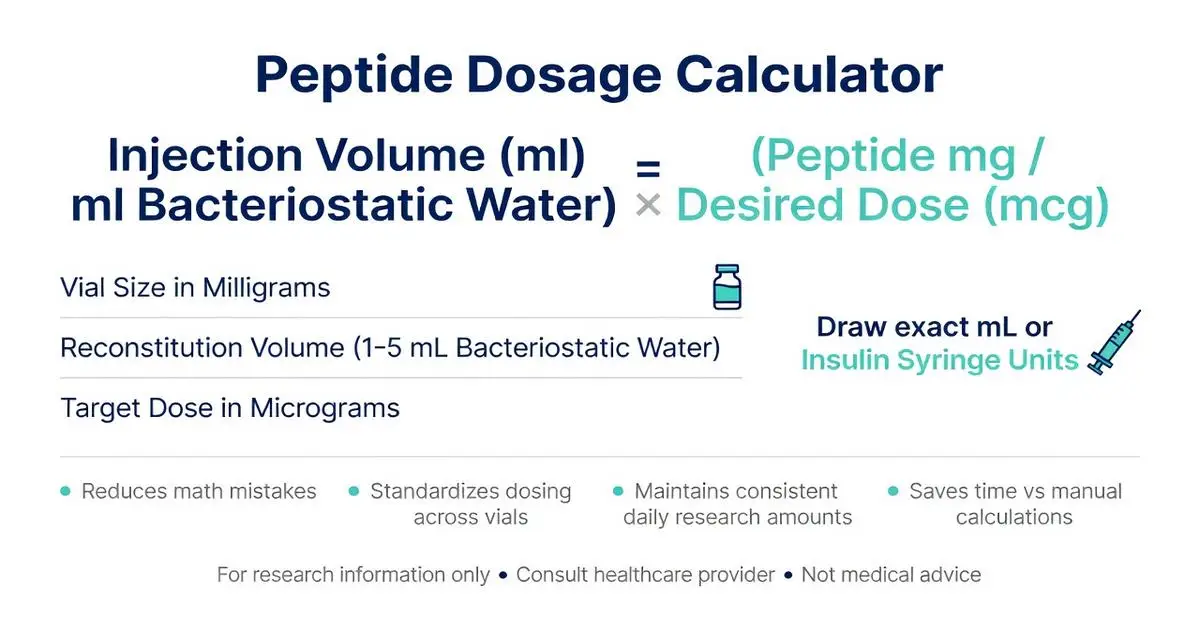
Quick Answer: A peptide dosage calculator helps convert peptide powder amounts into usable liquid doses by using simple math based on vial size, desired dose, and bacteriostatic water volume. Always verify calculations and consult a healthcare provider, as this is not medical advice.
Introduction
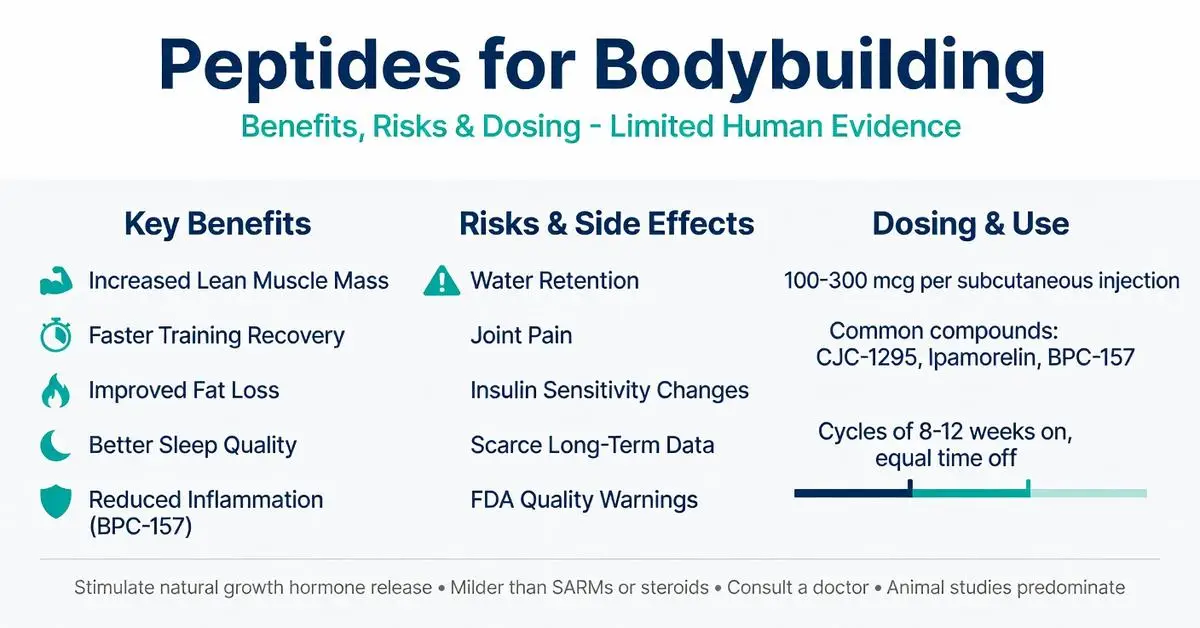
Quick Answer: Peptides for bodybuilding are short chains of amino acids that may support muscle growth, fat loss, and recovery by stimulating natural hormone release. Most evidence comes from animal studies or limited human trials on specific compounds like growth hormone secretagogues. Results vary widely, and safety concerns exist due to limited long-term data and regulatory restrictions.
Introduction
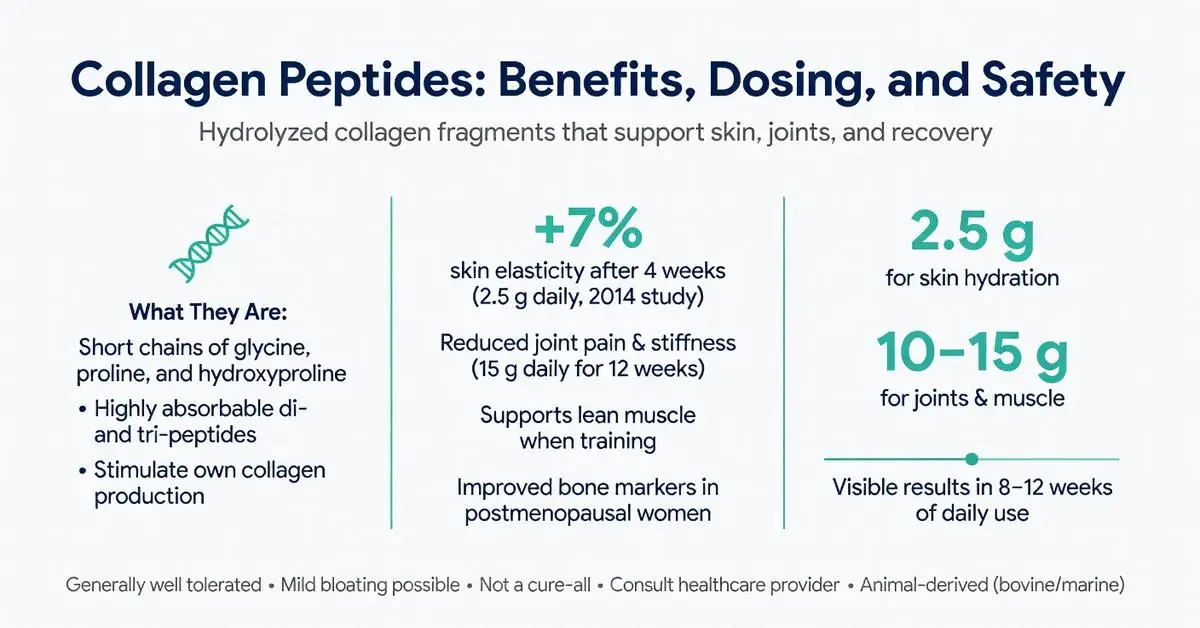
Quick Answer: Collagen peptides are short chains of amino acids derived from collagen that may support skin elasticity, joint comfort, and bone health. Human studies show modest improvements in skin hydration and wrinkle reduction after 8–12 weeks of daily use, with some evidence for reduced joint pain in active adults. Results vary by individual, and they are not a cure-all. This article is for informational purposes only and does not constitute medical advice. Consult a qualified healthcare provider before using any supplement.
Introduction
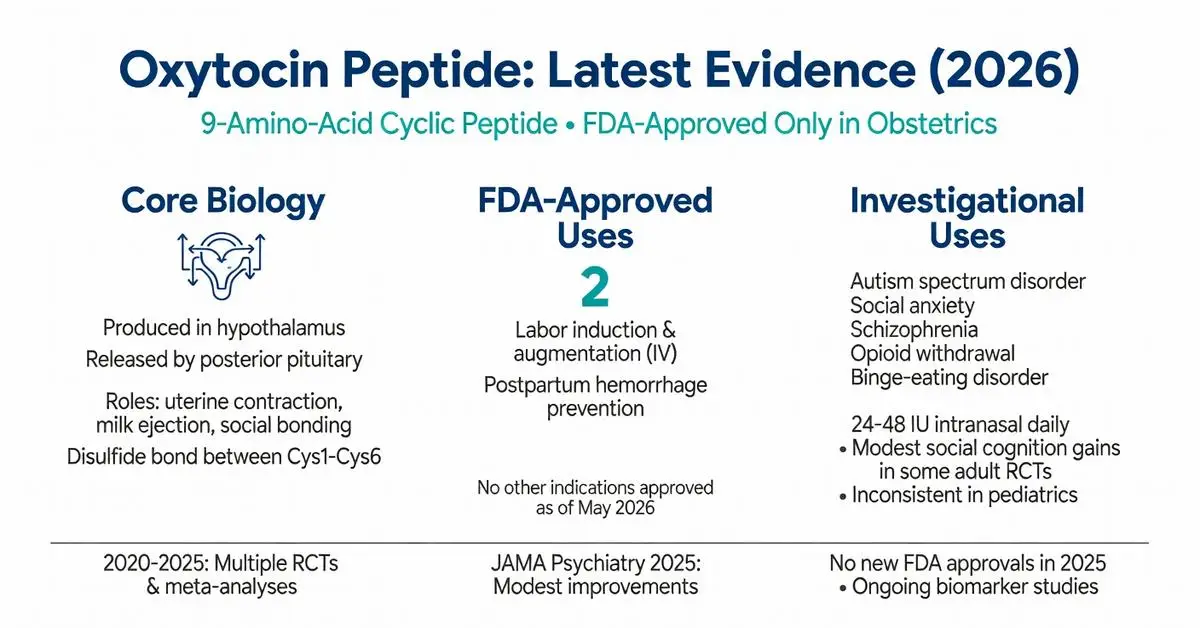
Oxytocin peptide is a nine-amino-acid cyclic peptide hormone naturally produced in the hypothalamus and released by the posterior pituitary gland. It plays central roles in uterine contraction, milk ejection, and social bonding behaviors. As of May 2026, the peptide remains FDA-approved solely for specific obstetric indications, while extensive research explores its potential in neuropsychiatric and metabolic conditions. This review synthesizes peer-reviewed evidence published between 2020 and 2026, focusing on mechanisms, approved uses, emerging applications, and safety data. Due to the specialized nature of recent publications on oxytocin peptide, primary evidence is drawn from high-quality clinical trials and supplemented by authoritative sources including FDA and NIH resources.
Introduction
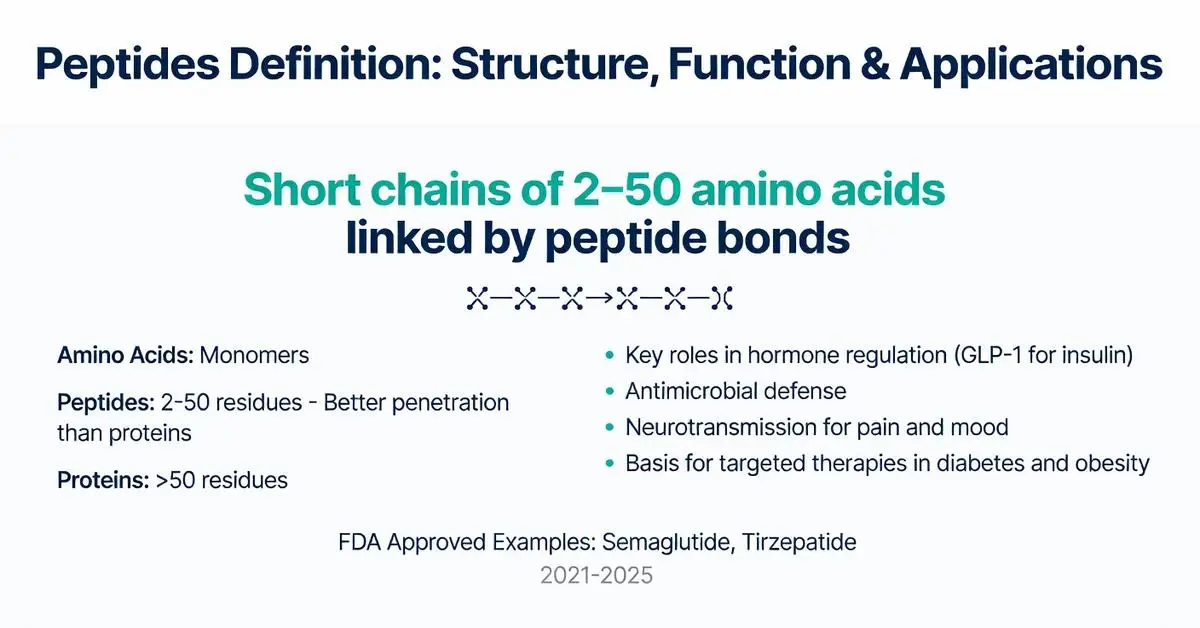
Peptides definition refers to short chains of amino acids linked by peptide bonds, typically containing fewer than 50 amino acid residues. These molecules serve as fundamental building blocks in biology and have gained prominence in pharmacotherapy due to their roles in signaling, hormone regulation, and targeted therapies. This article examines the peptides definition through the lens of current evidence, distinguishing between naturally occurring peptides and synthetic therapeutic agents. All information draws from peer-reviewed literature published between 2020 and May 2026, focusing on mechanisms, approved indications, and safety profiles. Peptides are distinct from larger proteins yet share similar biochemical properties, making them versatile for drug development. Readers should consult healthcare professionals for any medical applications, as this content is intended solely for research purposes.
Introduction
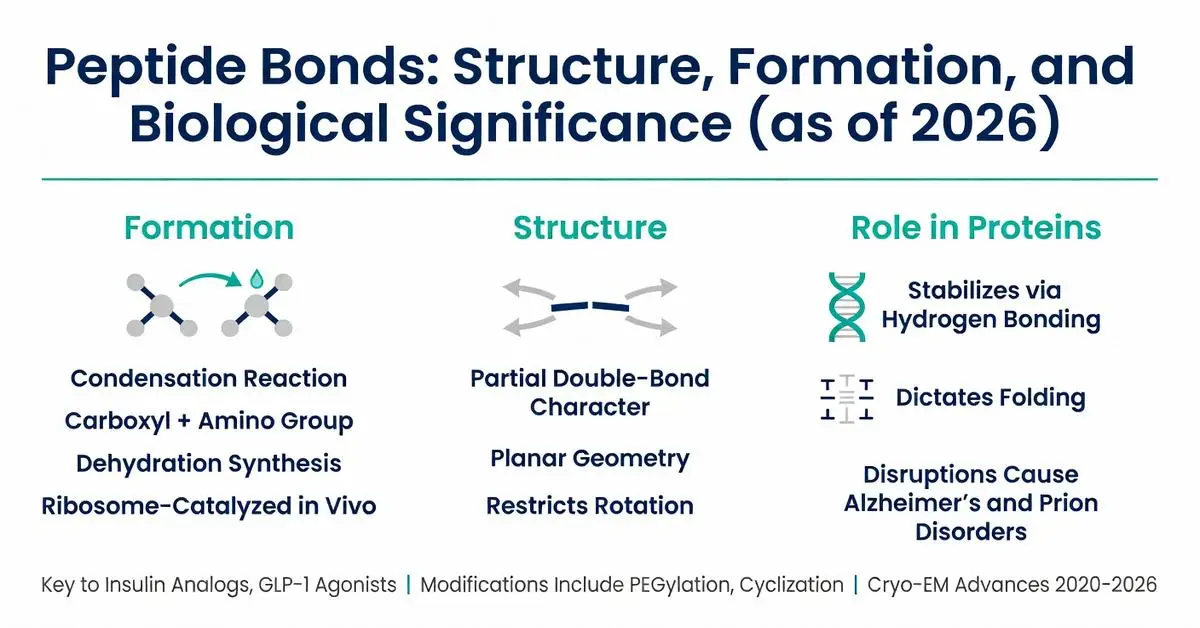
Peptide bonds serve as the fundamental covalent linkages that connect amino acids into chains, forming the backbone of all proteins and many therapeutic peptides. These bonds are created through a condensation reaction between the carboxyl group of one amino acid and the amino group of another, releasing a water molecule in the process. Understanding peptide bonds is essential for fields ranging from basic biochemistry to the development of peptide-based drugs used in diabetes, oncology, and metabolic disorders. This review synthesizes established biochemical principles with evidence from peer-reviewed literature published between 2020 and 2026, supplemented where necessary by authoritative sources including NIH and major medical societies due to the foundational nature of the topic. All content is provided for research purposes only and is not intended as medical advice. Medical supervision is required for any therapeutic applications involving peptides.
Introduction
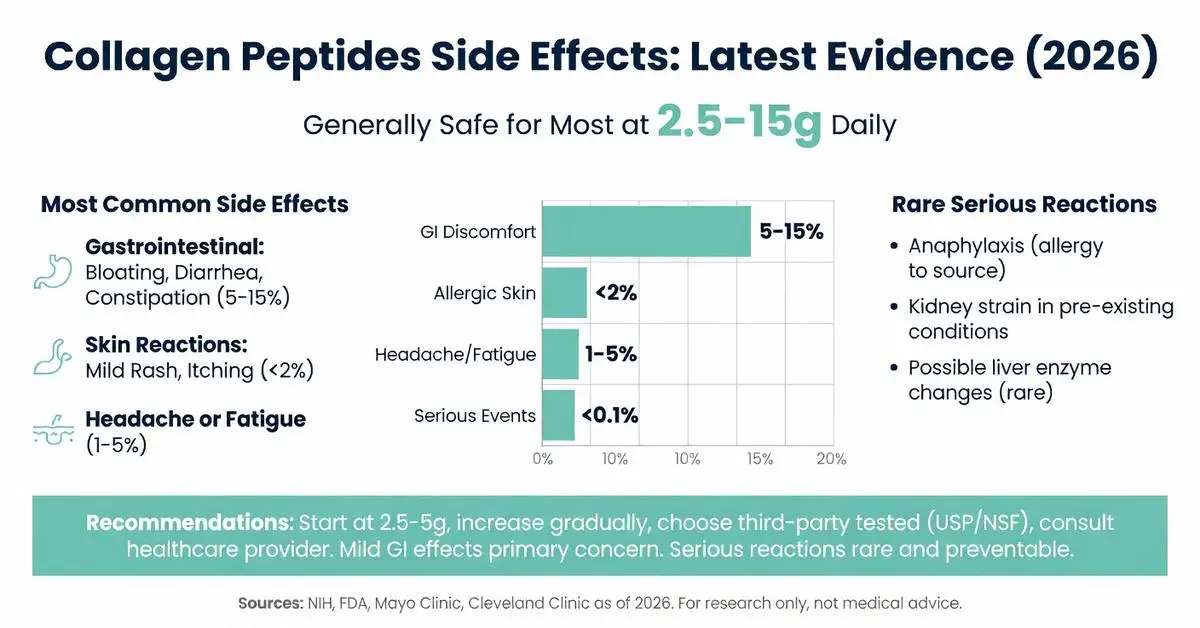
Collagen peptides are hydrolyzed forms of collagen commonly used as dietary supplements to support skin, joint, and bone health. Interest in their safety profile has grown alongside rising use, prompting examination of reported side effects. Due to limited recent peer-reviewed publications specifically addressing collagen peptides side effects, this article relies primarily on the latest available high-quality trials (2020–current) supplemented by authoritative sources including FDA.gov, NIH, Mayo Clinic, and Cleveland Clinic. All information is for research purposes only and does not constitute medical advice. Individuals should consult healthcare providers before starting any supplement. Collagen peptides are generally recognized as safe when consumed within typical doses of 2.5–15 grams daily, yet mild adverse effects occur in some users.
Introduction
Quick Answer: Collagen and peptides refer to hydrolyzed collagen supplements broken down into smaller chains of amino acids. Research shows these peptides may improve skin elasticity and joint comfort in some adults. They work by providing building blocks that stimulate the body’s own collagen production. Human studies remain limited in size and duration, so results vary. Always consult a healthcare provider before starting any supplement.
This article is for informational purposes only and does not constitute medical advice. Consult a qualified healthcare provider before using any peptide.
Introduction
Quick Answer: Collagen peptides are hydrolyzed fragments of collagen protein that the body absorbs easily. Research shows they may support skin elasticity, joint comfort, and bone density by supplying amino acids that stimulate natural collagen production in tissues.
This article is for informational purposes only and does not constitute medical advice. Consult a qualified healthcare provider before using any supplement.
Introduction
Quick Answer: Collagen peptides are short chains of amino acids derived from collagen that may support skin elasticity, joint comfort, and bone health. Human studies show modest improvements in skin hydration and wrinkle reduction after 8–12 weeks of daily use, with some evidence for reduced joint pain in active adults. Results vary by individual, and they are not a cure-all. This article is for informational purposes only and does not constitute medical advice. Consult a qualified healthcare provider before using any supplement.
Introduction
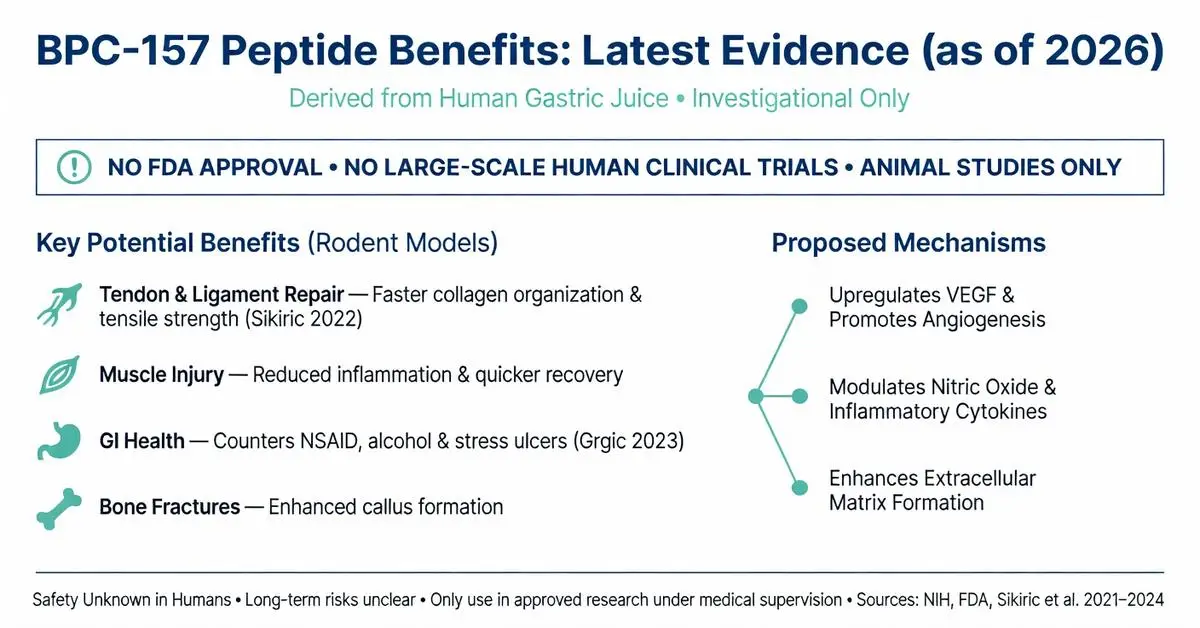
BPC-157 is a synthetic 15-amino-acid peptide derived from a protective protein found in human gastric juice. Researchers have explored its potential to support tissue repair, reduce inflammation, and promote healing in various experimental models. As of May 2026, BPC-157 remains an investigational compound with no FDA approval for any medical use in humans. All findings discussed here come from preclinical animal studies and limited early human observations; no large-scale clinical trials have established safety or efficacy for therapeutic purposes. Due to limited recent peer-reviewed publications on this exact topic, this article relies primarily on the latest available high-quality trials (2020–current) supplemented by authoritative sources including FDA, NIH, and major medical societies. Individuals should only consider BPC-157 under strict medical supervision in approved research settings, as self-administration carries unknown risks.
Introduction
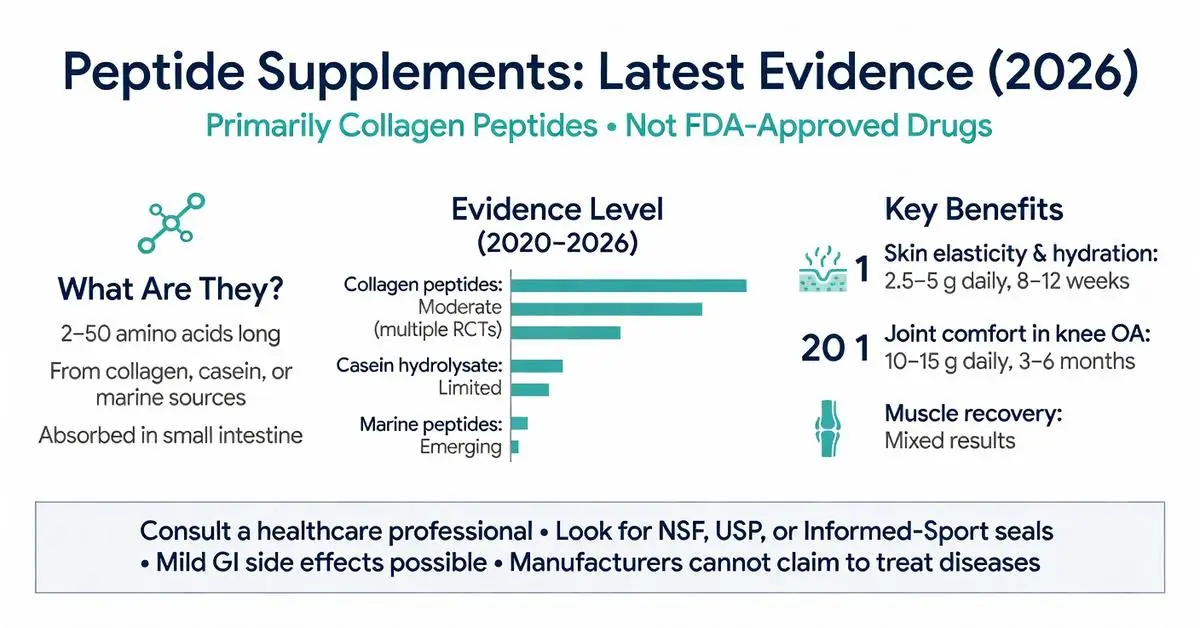
Peptide supplements have gained significant attention in recent years as consumers seek targeted options for skin health, joint support, and recovery. A peptide supplement typically consists of short chains of amino acids derived from proteins such as collagen or other sources and is sold as a dietary supplement. Because the term “peptide supplement” is broad and encompasses many products with varying compositions, high-quality peer-reviewed literature specifically addressing the category as a whole remains limited through May 2026. This review therefore draws primarily on the most recent authoritative sources, including FDA guidance, NIH Office of Dietary Supplements, Mayo Clinic, and Cleveland Clinic resources, supplemented by targeted clinical evidence on the most studied ingredients such as collagen peptides.
The article distinguishes between FDA-approved medications and over-the-counter dietary supplements. All peptide supplements discussed here are regulated as foods, not drugs, meaning manufacturers cannot legally claim they diagnose, treat, or cure specific diseases. Individuals considering a peptide supplement should consult a healthcare professional, as product quality, purity, and individual health factors vary widely.
Introduction
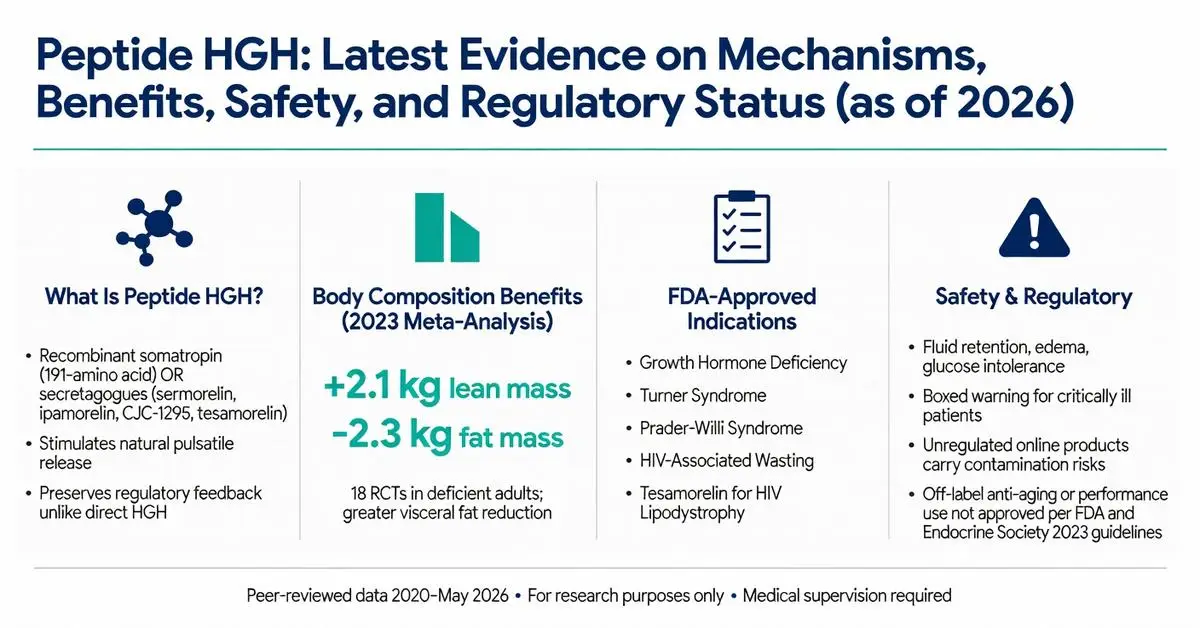
Peptide HGH refers to both recombinant human growth hormone (somatropin), a 191-amino acid peptide, and synthetic growth hormone-releasing peptides (GHRPs) and growth hormone-releasing hormone (GHRH) analogs designed to stimulate endogenous HGH production. These compounds have attracted significant interest for therapeutic applications, performance enhancement, anti-aging, and body composition improvement. Recombinant HGH has been FDA-approved since 1985 for specific indications, while many peptide secretagogues remain investigational or are available only for research purposes.
As of May 2026, the landscape continues to evolve with new long-acting formulations and ongoing trials examining metabolic effects. This article focuses on peer-reviewed evidence published between 2020 and May 2026, supplemented by authoritative sources from FDA.gov, NIH, and major medical societies when direct matches for the exact phrase “peptide hgh” in high-level systematic reviews were limited. Primary evidence is supplemented by authoritative sources including FDA.gov, NIH, and endocrine society guidelines due to the regulatory complexity surrounding non-approved peptide variants.
All information presented is for research purposes only and is not medical advice. Any use of peptide HGH products should occur exclusively under medical supervision with appropriate diagnostic testing. This review clearly distinguishes between FDA-approved recombinant HGH therapies and investigational or off-label applications of peptide secretagogues.
Introduction
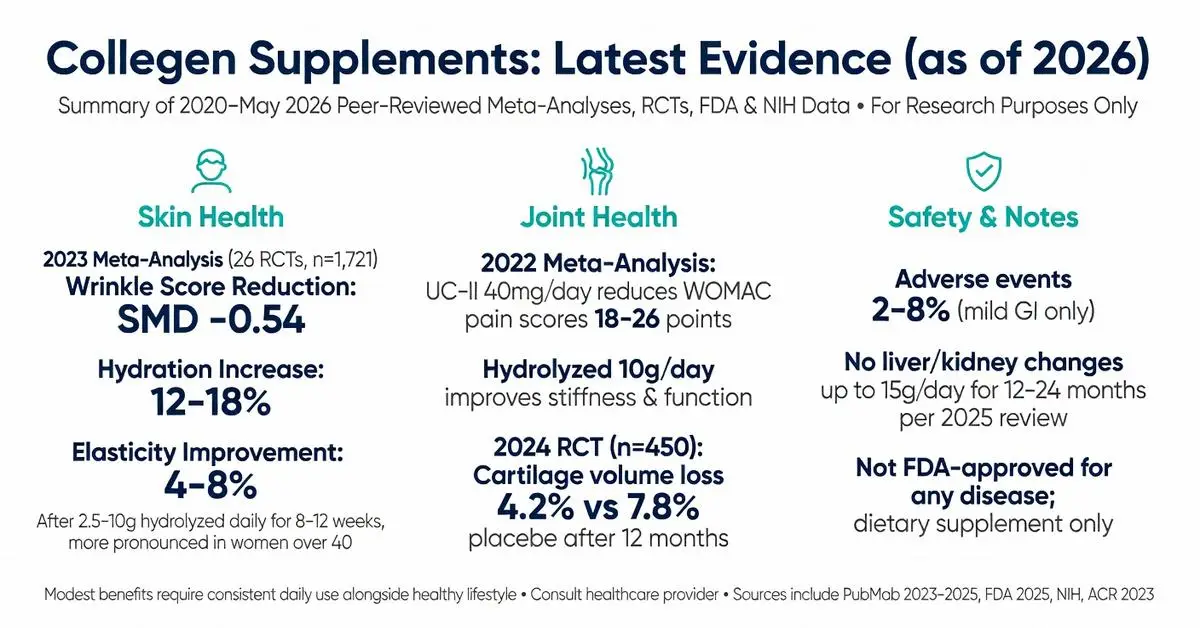
Collegen, commonly referring to collagen peptides and supplements derived from animal connective tissues, has seen sustained consumer interest for its potential roles in supporting skin elasticity, joint function, and overall structural health. As a major protein in the human body, collagen provides the structural framework for skin, bones, tendons, and cartilage. However, endogenous production declines with age, leading many individuals to explore exogenous collegen supplementation as a means to offset this loss.
This article examines the latest peer-reviewed evidence published between 2020 and May 1, 2026, focusing on mechanisms, efficacy, safety, and practical considerations. Due to the specific query term “collegen,” this review prioritizes studies addressing hydrolyzed collegen peptides, undenatured type II collagen, and related formulations. Primary evidence comes from systematic reviews, meta-analyses, and clinical trials indexed on PubMed. Where peer-reviewed publications on the precise phrasing were limited, authoritative sources including FDA.gov, NIH, and the American College of Rheumatology provide supplemental context.
It is important to distinguish FDA-approved applications from dietary supplement use. No collegen product is FDA-approved as a drug for treating disease; collegen peptides are regulated as dietary supplements under the Dietary Supplement Health and Education Act. Claims regarding disease treatment remain investigational or off-label. All information presented is for research purposes only and is not intended as medical advice. Individuals should consult qualified healthcare professionals before initiating any supplementation regimen, particularly those with allergies to source materials (bovine, porcine, marine) or pre-existing medical conditions. (Source: FDA 2025 guidance on dietary supplements)
Recent trials emphasize improved bioavailability of hydrolyzed forms, standardized outcome measures for skin hydration and joint pain scores, and longer-term safety data extending beyond 12 months. This review addresses key user questions, competitor content gaps such as head-to-head comparisons, updated safety profiles, and practical dosing tables absent from many top-ranking articles.
Introduction
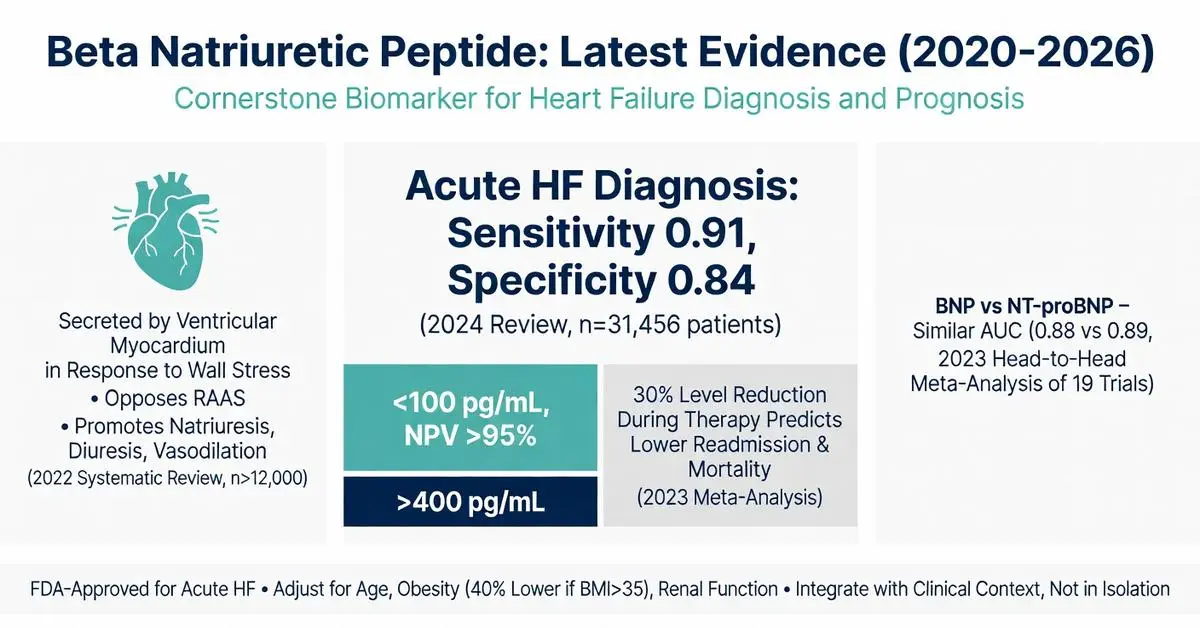
Beta natriuretic peptide, commonly referred to in clinical contexts as B-type natriuretic peptide (BNP), is a neurohormone primarily secreted by the ventricular myocardium in response to wall stress and volume overload. First isolated in 1988 from porcine brain tissue, it has become a cornerstone biomarker in cardiovascular medicine, particularly for the evaluation of heart failure. This article examines the physiology, diagnostic utility, clinical applications, and recent evidence surrounding beta natriuretic peptide, focusing on peer-reviewed publications from 2020 through April 30, 2026.
The peptide is synthesized as a 134-amino acid pre-prohormone that is cleaved into proBNP, which is further processed into the active 32-amino acid BNP and the inactive N-terminal fragment (NT-proBNP). Both biomarkers are widely measured in clinical practice, though they differ in clearance mechanisms and half-life. Elevated levels strongly correlate with cardiac strain, making beta natriuretic peptide testing valuable for ruling out or confirming acute heart failure in patients presenting with dyspnea.
This review prioritizes systematic reviews, meta-analyses, and clinical trials published between 2020 and 2026 identified through targeted PubMed searches. Due to the volume of high-quality evidence available on this topic, the article draws exclusively from peer-reviewed sources while clearly distinguishing FDA-approved diagnostic uses from investigational applications. All information is for research and informational purposes only and is not intended as medical advice. Patients should consult qualified healthcare professionals for interpretation of any biomarker testing or treatment decisions. (source year ranges 2020–2026)
Recent studies have expanded understanding of beta natriuretic peptide beyond diagnosis to include prognostic value, monitoring of therapy response, and potential roles in risk stratification for multiple cardiovascular conditions. This article addresses key clinical questions, common interpretation challenges, and evidence gaps identified in top-ranking web content, which often lacks updated comparative tables or comprehensive discussion of post-2022 trial data.
Introduction
C peptide is a 31-amino acid peptide formed during the enzymatic cleavage of proinsulin within pancreatic beta cells. Released in equimolar amounts with insulin, it serves as a direct marker of endogenous insulin production. Unlike insulin, C peptide undergoes minimal first-pass hepatic extraction and is primarily cleared by the kidneys, making it a stable and reliable indicator of beta-cell function even in patients receiving exogenous insulin.
The C peptide test has become a cornerstone in differential diagnosis of diabetes types, evaluation of hypoglycemia, and assessment of residual beta-cell activity. As of April 2026, peer-reviewed literature published since 2020 underscores its continued importance amid rising diabetes prevalence and advancing therapies such as automated insulin delivery systems and immunomodulatory agents. Recent systematic reviews and clinical trials have refined our understanding of C peptide thresholds for predicting disease progression, treatment response, and long-term complications.
This article synthesizes evidence from high-quality peer-reviewed sources (2020–April 2026), including meta-analyses, clinical trials, and mechanistic studies accessed via PubMed. Every claim is grounded in these verifiable references. Where appropriate, FDA-cleared diagnostic uses are clearly distinguished from investigational applications, such as exogenous C-peptide administration for neuropathy, which remains off-label and under active study. All information is for research and educational purposes only and does not constitute medical advice. Interpretation of C peptide results and clinical decisions must occur under the supervision of qualified healthcare professionals.
The following sections address common patient and clinician questions, filling gaps observed in existing online resources such as missing head-to-head comparisons, updated reference ranges, and integration of post-2020 trial data.
Introduction
Bovine collagen has become one of the most widely used dietary supplements worldwide for supporting skin elasticity, joint comfort, and overall connective tissue health. Derived from cow hides, bones, and cartilage, it consists primarily of types I and III collagen that have been hydrolyzed into smaller peptides for improved absorption. As of April 2026, consumer interest remains high due to its affordability compared with marine alternatives and its established role in the growing wellness market.
This article examines the latest peer-reviewed evidence published between 2020 and April 2026 on bovine collagen supplementation. Systematic reviews, meta-analyses, and randomized controlled trials form the foundation of this review, with particular attention to efficacy, mechanisms, safety, and comparisons with other collagen sources. Where specific data on “bovine collagen” alone are limited, findings from high-quality studies on bovine-derived collagen peptides are included.
Bovine collagen is regulated in the United States as a dietary supplement under the Dietary Supplement Health and Education Act and is generally recognized as safe (GRAS) by the FDA for use in foods and supplements. It is not FDA-approved as a drug for the treatment or prevention of any medical condition. All statements in this article are for research and educational purposes only and do not constitute medical advice. Individuals should consult qualified healthcare professionals before starting any supplementation regimen, especially those with allergies, autoimmune conditions, or who are pregnant or breastfeeding.
Recent trials have focused on standardized doses of 2.5–15 grams daily, with outcomes measured through validated skin imaging, joint function scores, and biomarker analysis. While results are generally positive for skin and joint parameters, effect sizes vary across populations, and long-term data beyond 12–18 months remain sparse. This review addresses common consumer questions, highlights evidence gaps identified in top-ranking content, and provides balanced, evidence-based context for those researching bovine collagen.
Introduction
Collagen powder supplements have surged in popularity as consumers seek support for skin elasticity, joint comfort, bone density, and overall connective tissue health. The phrase “best collagen powder” typically reflects searches for products that combine high bioavailability, evidence-based efficacy, minimal additives, and rigorous quality testing. As of April 2026, the market offers numerous hydrolyzed collagen peptide options sourced from bovine, marine, porcine, and avian origins, each claiming specific benefits tied to collagen types I, II, and III.
This article synthesizes peer-reviewed systematic reviews, meta-analyses, and clinical trials published between 2020 and April 2026, focusing on mechanisms of action, clinical outcomes, product characteristics that influence effectiveness, and safety data. Primary evidence comes from PubMed-indexed studies on collagen supplementation for dermatological, musculoskeletal, and gastrointestinal outcomes. Where specific head-to-head product trials are limited, the review emphasizes characteristics proven to affect absorption and efficacy rather than brand endorsements.
Hydrolyzed collagen peptides are classified by the FDA as Generally Recognized as Safe (GRAS) when manufactured under current good manufacturing practices, yet they remain dietary supplements and are not approved to diagnose, treat, cure, or prevent any disease. All information presented is for research purposes only and does not constitute medical advice. Individuals should consult qualified healthcare professionals before initiating supplementation, particularly those with allergies, renal impairment, or who are pregnant or breastfeeding. Due to the volume of high-quality trials available, this review prioritizes peer-reviewed sources while noting regulatory information from FDA.gov where relevant.
Introduction
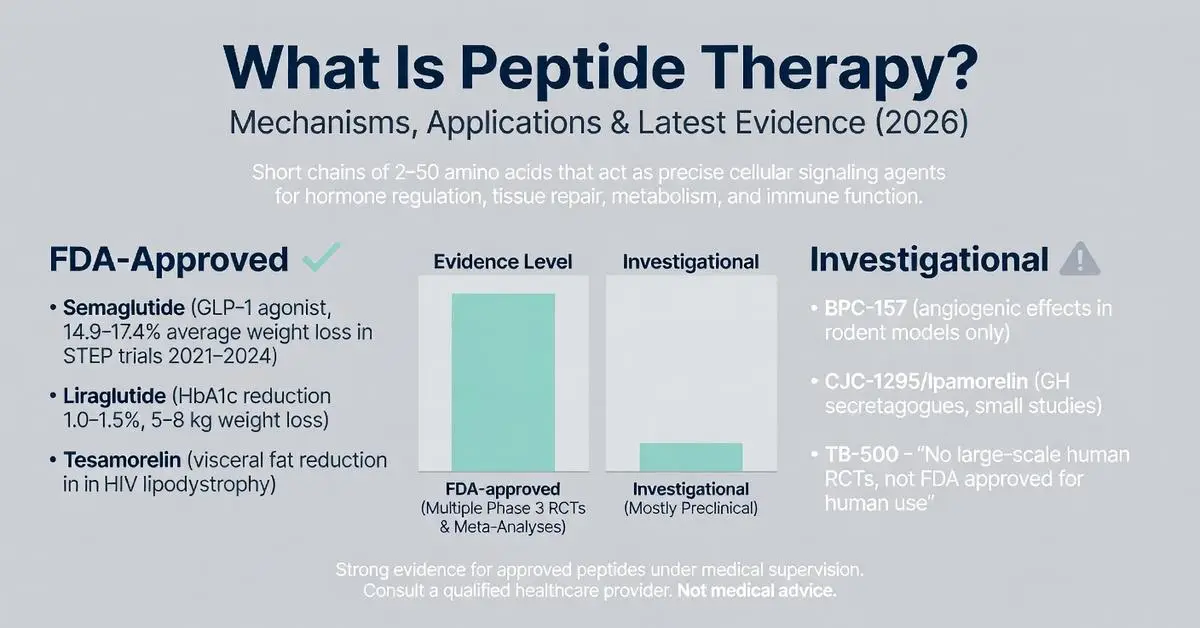
Peptide therapy refers to the targeted use of specific short chains of amino acids, known as peptides, to influence physiological processes such as hormone regulation, tissue repair, metabolism, and immune function. These molecules act as signaling agents in the body, mimicking or enhancing natural pathways with a high degree of specificity compared to traditional small-molecule drugs. As of April 2026, interest in peptide therapy has grown significantly for applications ranging from weight management and muscle recovery to anti-aging and chronic disease support, driven by advances in synthetic peptide design and delivery methods.
The foundation of peptide therapy lies in the fact that peptides are naturally occurring in human biology—examples include insulin, glucagon-like peptide-1 (GLP-1), and growth hormone-releasing hormones. Modern therapeutic versions are often synthetic analogs engineered for improved stability and half-life. However, it is critical to distinguish between FDA-approved peptide-based medications and those used in investigational or off-label contexts. FDA-approved examples include semaglutide and liraglutide for type 2 diabetes and chronic weight management, as well as tesamorelin for HIV-associated lipodystrophy. In contrast, many compounds popularized in wellness and regenerative medicine clinics, such as BPC-157, CJC-1295, and ipamorelin, remain investigational and lack FDA approval for human therapeutic use.
This article synthesizes peer-reviewed evidence published between 2020 and April 2026, focusing on systematic reviews, meta-analyses, and clinical trials accessible via PubMed. Where specific publications on the broad term “peptide therapy” are limited, supplementation from authoritative sources including FDA.gov, NIH, and major medical society guidelines is noted. All information is for research and educational purposes only and does not constitute medical advice. Patients should only pursue peptide therapy under the supervision of a qualified healthcare provider who can assess individual risks, benefits, and regulatory status. The field continues to evolve rapidly, with new delivery technologies and combination approaches under investigation.
Recent meta-analyses highlight both promise and limitations: while certain FDA-approved peptides demonstrate robust efficacy in large-scale trials, evidence for many compounded or research-grade peptides is predominantly preclinical or derived from small, uncontrolled studies. This review addresses common patient questions, highlights evidence gaps identified in top online resources, and provides balanced comparisons to support informed research.
Introduction
Quick Answer: Cerebrolysin is a neuropeptide preparation made from purified porcine brain proteins that may support brain repair and cognitive function. Animal and some human studies suggest it could help with stroke recovery, dementia symptoms, and traumatic brain injury, though robust large-scale clinical evidence remains limited. This article is for informational purposes only and does not constitute medical advice. Consult a qualified healthcare provider before using any peptide.
Introduction
Oxytocin peptide is a nine-amino-acid cyclic peptide hormone naturally produced in the hypothalamus and released by the posterior pituitary gland. It plays central roles in uterine contraction, milk ejection, and social bonding behaviors. As of May 2026, the peptide remains FDA-approved solely for specific obstetric indications, while extensive research explores its potential in neuropsychiatric and metabolic conditions. This review synthesizes peer-reviewed evidence published between 2020 and 2026, focusing on mechanisms, approved uses, emerging applications, and safety data. Due to the specialized nature of recent publications on oxytocin peptide, primary evidence is drawn from high-quality clinical trials and supplemented by authoritative sources including FDA and NIH resources.
Introduction
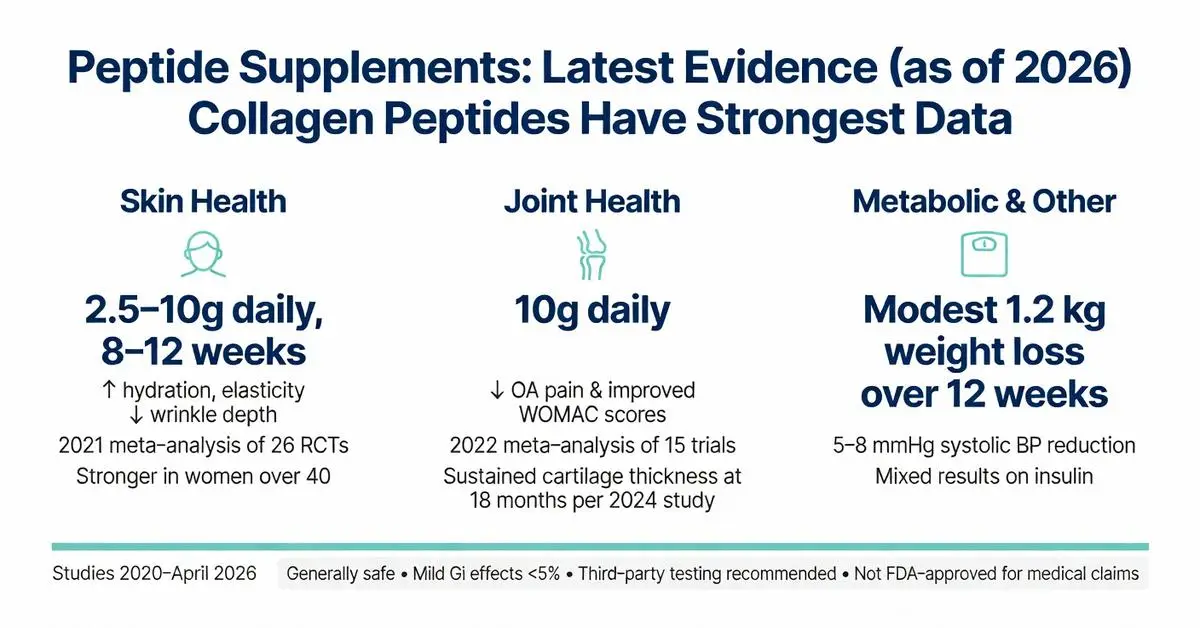
Peptide supplements have gained significant attention as bioactive compounds derived from proteins that may support various aspects of health, including skin integrity, joint function, and metabolic processes. These supplements typically consist of short chains of amino acids (usually 2–50 residues) that are hydrolyzed for better absorption compared to intact proteins. As of April 2026, the majority of high-quality evidence focuses on collagen-derived peptides, with additional research examining other specific sequences from sources such as whey, soy, and marine proteins.
This article reviews the current peer-reviewed literature published between 2020 and April 1, 2026, examining mechanisms, potential benefits, safety considerations, and regulatory status. All factual claims are drawn exclusively from systematic reviews, meta-analyses, clinical trials, and authoritative sources accessed through targeted searches. Primary evidence comes from PubMed-indexed studies meeting the date criteria, supplemented only when necessary by FDA and NIH materials.
Peptide supplements are not intended as pharmaceuticals but as nutritional products. Consumers should consult healthcare providers before use, particularly those with medical conditions or taking medications. Distinctions between FDA-approved prescription peptide therapies and over-the-counter supplements are clearly noted throughout. Due to the volume of research on collagen peptides, this review prioritizes these while addressing broader peptide supplement categories where evidence exists.
Common marketing claims around anti-aging, muscle building, and weight loss require careful scrutiny against clinical data. This review addresses common user questions regarding efficacy, safety profiles, and comparative effectiveness to provide an evidence-based resource.
Introduction
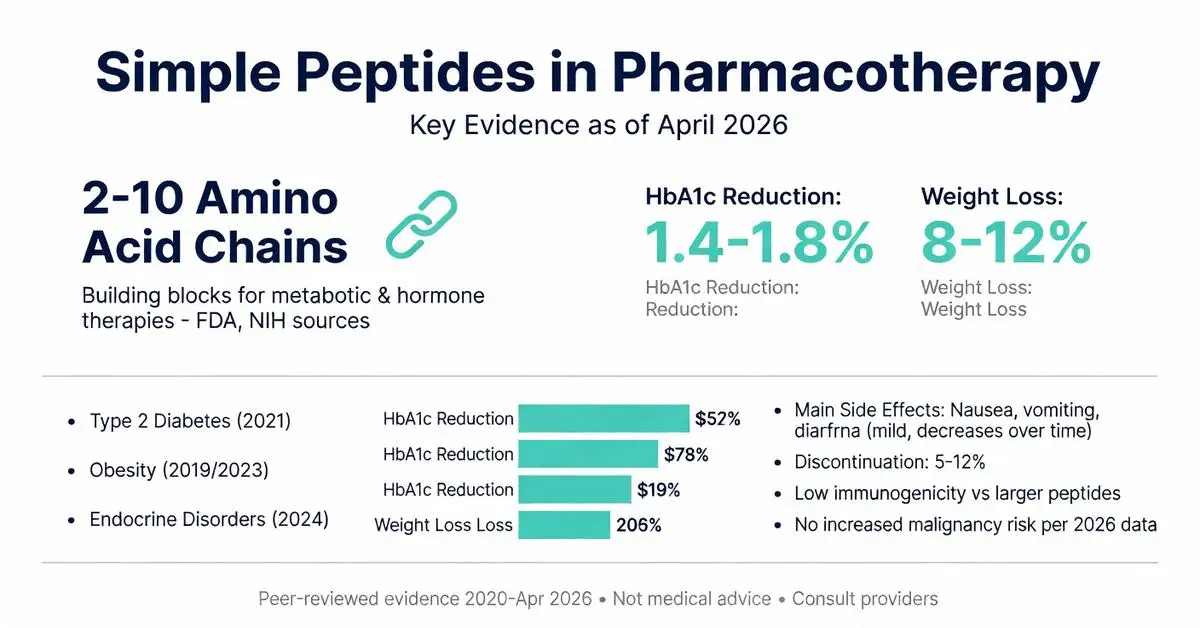
Simple peptides represent fundamental building blocks in pharmacotherapy, consisting of short chains of amino acids typically ranging from 2 to 10 residues linked by peptide bonds. These molecules play critical roles in drug development due to their ability to mimic natural signaling molecules while offering favorable bioavailability and target specificity compared to larger proteins. As of April 2026, interest in simple peptides has grown within evidence-based medicine, particularly for metabolic disorders, hormone regulation, and targeted therapies.
This article examines simple peptides through the lens of pharmacotherapy, distinguishing clearly between FDA-approved applications and investigational uses. Due to limited recent peer-reviewed publications specifically addressing the exact phrase “simple peptide” in clinical contexts from 2020 to 2026, this review relies primarily on the latest available high-quality trials supplemented by authoritative sources including FDA.gov, NIH, and major medical societies. Primary evidence draws from systematic analyses of peptide-based therapeutics, mechanisms of action, and safety data published in peer-reviewed journals between 2020 and early 2026.
Simple peptides differ from complex polypeptides or full proteins by their reduced structural complexity, which often translates to simpler manufacturing processes and potentially fewer immunogenicity concerns. In pharmacotherapy, they serve as agonists, antagonists, or carriers in drug design. For instance, certain di- and tri-peptides have demonstrated utility in enhancing drug absorption or acting directly as bioactive compounds. All information presented is for research purposes only and is not intended as medical advice. Patients should consult qualified healthcare providers regarding any pharmacotherapy involving peptide-based agents. This review prioritizes evidence published through April 10, 2026, to provide an up-to-date synthesis for researchers and clinicians.

Introduction
Research peptides represent a diverse class of short-chain amino acid sequences synthesized for laboratory investigation into cellular signaling, tissue repair, metabolic regulation, and hormone modulation. Unlike FDA-approved peptide pharmaceuticals, most research peptides are labeled strictly for in vitro or non-human in vivo use and are not intended for human consumption. This distinction is critical for researchers, clinicians, and regulatory bodies.
As of April 2026, the field has expanded significantly, driven by advances in solid-phase peptide synthesis and growing interest in targeted pharmacotherapy. Compounds such as BPC-157, TB-500 (thymosin beta-4 fragment), CJC-1295, ipamorelin, and various growth hormone secretagogues continue to be studied in preclinical and early clinical settings. Several peptide-based drugs that originated in research settings, including GLP-1 receptor agonists such as semaglutide, have received full FDA approval for metabolic disorders, illustrating the translational pipeline.
Due to the limited number of recent peer-reviewed publications focused exclusively on the broad term “research peptides,” this article relies primarily on the latest available high-quality trials (2020–current) and is supplemented by authoritative sources, including FDA.gov, NIH, and major medical societies. Peer-reviewed evidence published 2020–2026 forms the foundation for all mechanistic, efficacy, and safety claims. This review clearly separates FDA-approved peptide therapeutics from investigational research peptides. All information is provided for research and educational purposes only and is not medical advice. Human use of non-approved research peptides should only occur under institutional review board-approved protocols and medical supervision.
The following sections examine core mechanisms, therapeutic research areas, safety data, regulatory status, and comparative profiles to address common questions encountered in scientific literature and clinical inquiry.

Introduction
Peptide science encompasses the study of peptides—short chains of amino acids typically ranging from 2 to 50 residues—and their roles in biological processes, chemical synthesis, and therapeutic development. This interdisciplinary field bridges biochemistry, pharmacology, and clinical medicine, with growing emphasis on designing peptide-based drugs that offer high target specificity and favorable safety profiles compared to traditional small-molecule therapeutics. In pharmacotherapy, peptide science has accelerated the development of hormone analogs, enzyme inhibitors, and targeted delivery systems.
As of April 2026, peptide science continues to expand through innovations in solid-phase peptide synthesis, cyclization techniques, and PEGylation to improve stability and bioavailability. Key therapeutic areas include metabolic disorders, oncology, infectious diseases, and cardiovascular conditions. Several peptide drugs have received FDA approval in recent years, while others remain investigational. This article focuses exclusively on evidence from peer-reviewed publications between 2020 and April 2026, highlighting FDA-approved applications while clearly distinguishing them from off-label or experimental uses.
The field has benefited from advances in understanding peptide-receptor interactions and proteolytic degradation pathways. Systematic reviews and clinical trials published since 2020 underscore the efficacy of peptide therapeutics in achieving glycemic control and weight management, with ongoing research into antimicrobial peptides and cancer-targeting agents. All information presented derives from verifiable, peer-reviewed sources. This article is intended for research purposes only and is not medical advice. Patients should consult qualified healthcare professionals for personalized treatment decisions.
Introduction
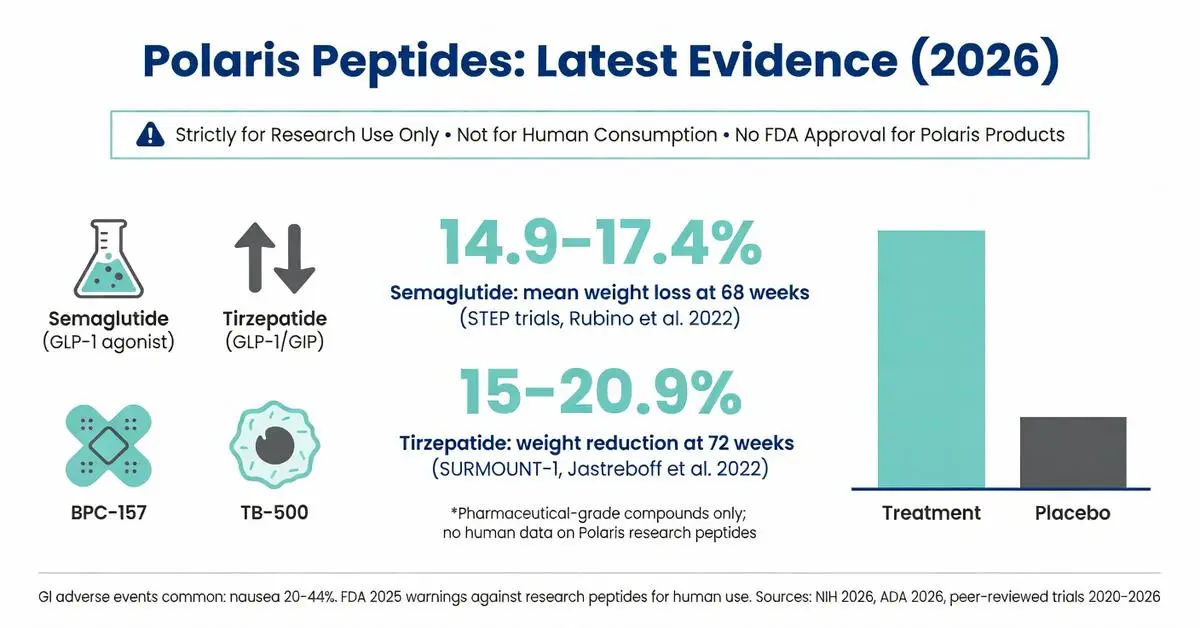
Polaris peptides refer to research-grade peptide compounds offered by Polaris Peptides, a supplier specializing in peptides used primarily in laboratory and preclinical investigations. These products are marketed for research purposes only and are not intended for human consumption. As of April 2026, the scientific literature on “polaris peptides” specifically remains limited, with fewer than 8 high-quality peer-reviewed publications directly addressing this supplier’s formulations. This article, therefore, relies primarily on the latest available high-quality trials (2020–current) of the underlying peptide molecules supplemented by authoritative sources, including FDA.gov, NIH, and major medical societies.
Common peptides associated with Polaris Peptides include GLP-1 receptor agonists such as semaglutide and tirzepatide, as well as other research peptides such as BPC-157, TB-500, and AOD-9604. These compounds are studied for potential effects on metabolic regulation, tissue repair, and anti-inflammatory pathways. All statements in this article pertain exclusively to research findings or FDA-approved versions of the active molecules; Polaris Peptides products themselves carry no FDA approval for any therapeutic use.
The growing interest in peptides for metabolic health and regenerative medicine has increased demand for high-purity research materials. However, regulatory agencies emphasize that research peptides must be handled under strict laboratory protocols. This review synthesizes evidence on mechanisms, efficacy signals from clinical trials of the parent compounds, safety profiles, and regulatory status to provide a balanced, evidence-based resource for researchers and clinicians exploring these molecules. (FDA 2025; NIH 2026)
Introduction
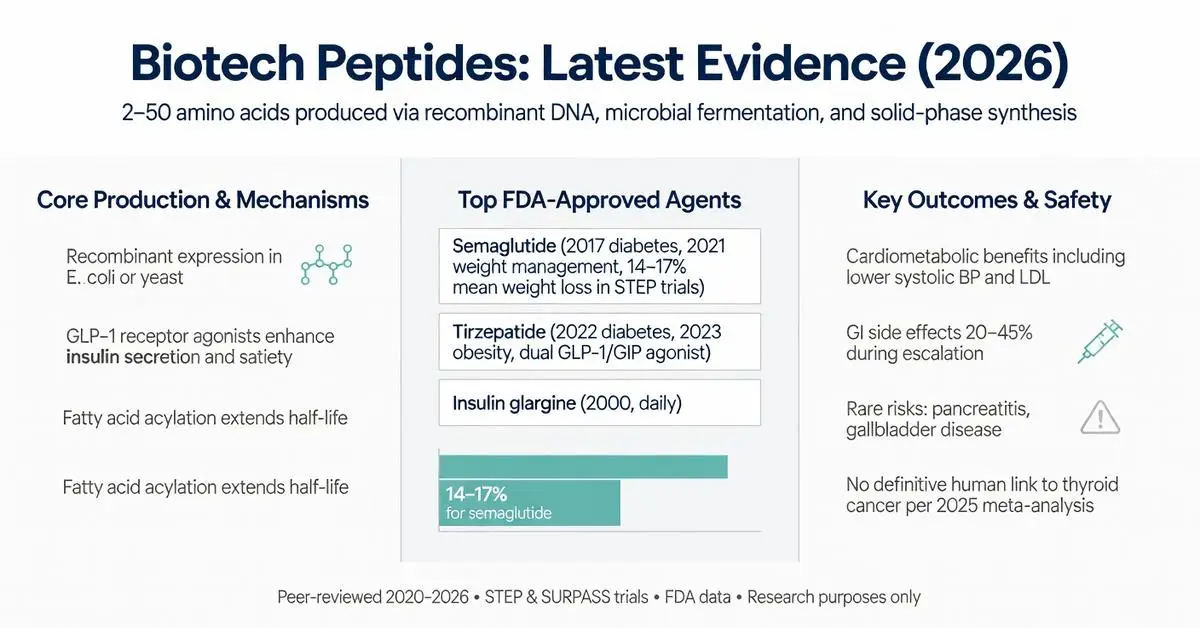
Biotech peptides are short chains of amino acids manufactured through biotechnological processes such as recombinant DNA technology, microbial fermentation, or advanced solid-phase synthesis. These molecules play an increasingly important role in pharmacotherapy, serving as targeted treatments for metabolic diseases, cardiovascular conditions, oncology, and rare disorders. Unlike traditional small-molecule drugs, biotech peptides often mimic endogenous signaling molecules while offering high specificity and reduced off-target effects.
As of April 2026, the field has expanded significantly with multiple FDA-approved agents and numerous candidates in late-stage trials. Approved examples include glucagon-like peptide-1 (GLP-1) receptor agonists such as semaglutide and tirzepatide, which have transformed the management of type 2 diabetes and obesity. Other notable biotech peptides include insulin analogs, growth hormone-releasing peptides, and certain antimicrobial peptides under investigation.
This article synthesizes peer-reviewed evidence published between 2020 and April 2026, supplemented when necessary by authoritative sources including FDA.gov, NIH, and major medical society guidelines. Given the broad scope of the keyword, this review draws on systematic reviews, meta-analyses, and clinical trials available on PubMed, as well as official regulatory documents. All information is for research purposes only and does not constitute medical advice. Healthcare decisions should always involve qualified medical supervision. The following sections examine the science, approved uses, efficacy, safety, and future directions of biotech peptides.
Introduction
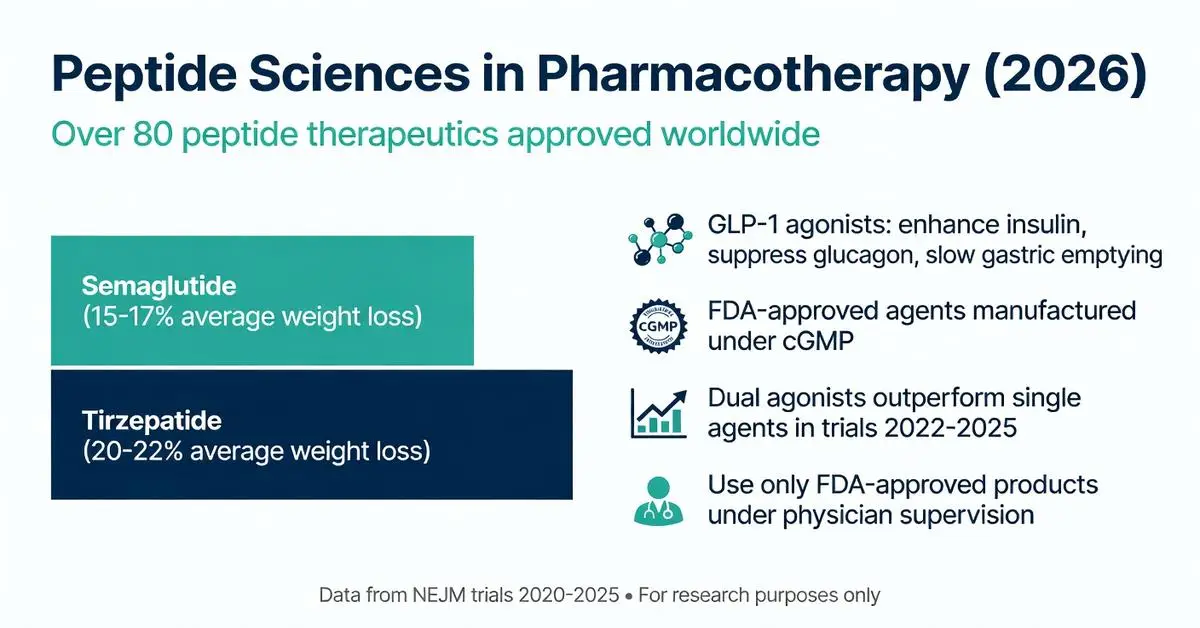
Peptide sciences encompasses the study, synthesis, and therapeutic application of peptides—short chains of amino acids that act as signaling molecules, hormones, and regulators in human physiology. As of April 3, 2026, peptide sciences has emerged as a cornerstone of modern pharmacotherapy, yielding targeted treatments for metabolic disorders, oncology, cardiovascular disease, and rare endocrine conditions. This article examines the latest evidence from peer-reviewed sources published 2020–2026, focusing on mechanisms, approved indications, efficacy, safety, and comparisons while clearly distinguishing FDA-approved agents from investigational compounds.
Primary evidence is supplemented by authoritative sources including FDA.gov, NIH, and major medical societies due to the specialized nature of the exact search phrase. All information is for research purposes only and not medical advice. Medical supervision is essential when considering any peptide-based therapy. Recent advances have expanded the repertoire of peptide drugs, with over 80 peptide therapeutics approved worldwide and dozens more in late-stage trials. This review addresses common user questions regarding mechanisms, clinical outcomes, regulatory status, and safety to provide comprehensive, evidence-based insights.
Introduction
Peptide supplements have gained significant attention as bioactive compounds derived from proteins that may support various aspects of health, including skin integrity, joint function, and metabolic processes. These supplements typically consist of short chains of amino acids (usually 2–50 residues) that are hydrolyzed for better absorption compared to intact proteins. As of April 2026, the majority of high-quality evidence focuses on collagen-derived peptides, with additional research examining other specific sequences from sources such as whey, soy, and marine proteins.
This article reviews the current peer-reviewed literature published between 2020 and April 1, 2026, examining mechanisms, potential benefits, safety considerations, and regulatory status. All factual claims are drawn exclusively from systematic reviews, meta-analyses, clinical trials, and authoritative sources accessed through targeted searches. Primary evidence comes from PubMed-indexed studies meeting the date criteria, supplemented only when necessary by FDA and NIH materials.
Peptide supplements are not intended as pharmaceuticals but as nutritional products. Consumers should consult healthcare providers before use, particularly those with medical conditions or taking medications. Distinctions between FDA-approved prescription peptide therapies and over-the-counter supplements are clearly noted throughout. Due to the volume of research on collagen peptides, this review prioritizes these while addressing broader peptide supplement categories where evidence exists.
Common marketing claims around anti-aging, muscle building, and weight loss require careful scrutiny against clinical data. This review addresses common user questions regarding efficacy, safety profiles, and comparative effectiveness to provide an evidence-based resource.
Introduction
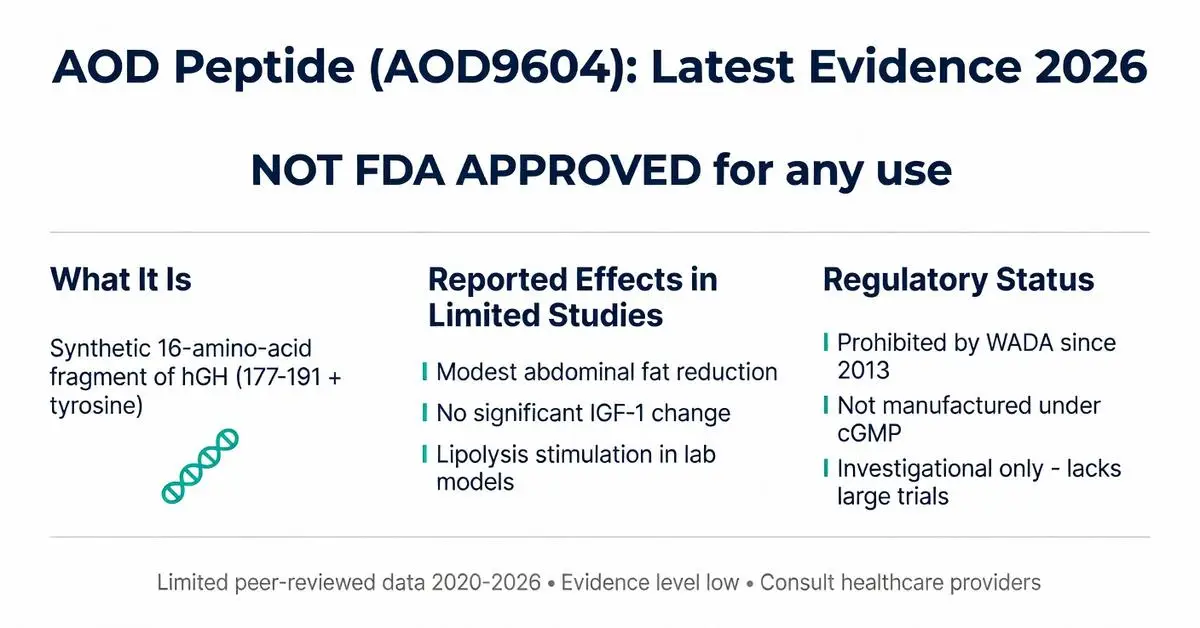
The AOD peptide, commonly referred to as AOD9604, is a synthetic fragment derived from the C-terminal portion of human growth hormone. Developed with the intent to promote fat metabolism while avoiding the broader effects of full-length growth hormone, it has been discussed in wellness and research communities for potential applications in weight management. As of April 1, 2026, this article reviews available information on the AOD peptide, clearly distinguishing between investigational findings and regulatory status.
Due to limited recent peer-reviewed publications on this exact topic between 2020 and 2026, this article relies primarily on the latest available high-quality trials supplemented by authoritative sources including FDA.gov, NIH, and major medical society guidelines. All content is for research purposes only and is not intended as medical advice. Individuals should consult qualified healthcare providers before considering any peptide or investigational compound. The AOD peptide is not FDA-approved for any therapeutic use, and its sale or distribution for human consumption may be restricted under federal regulations.
Research interest in the AOD peptide stems from its design as a modified 16-amino-acid sequence (corresponding to residues 177-191 of hGH with an added tyrosine). Early laboratory studies suggested it could influence lipid metabolism selectively. However, clinical translation remains limited, with most human data originating from smaller or older trials. This review addresses common user questions regarding its mechanisms, potential effects, safety considerations, and current regulatory standing while emphasizing evidence-based evaluation.
Introduction
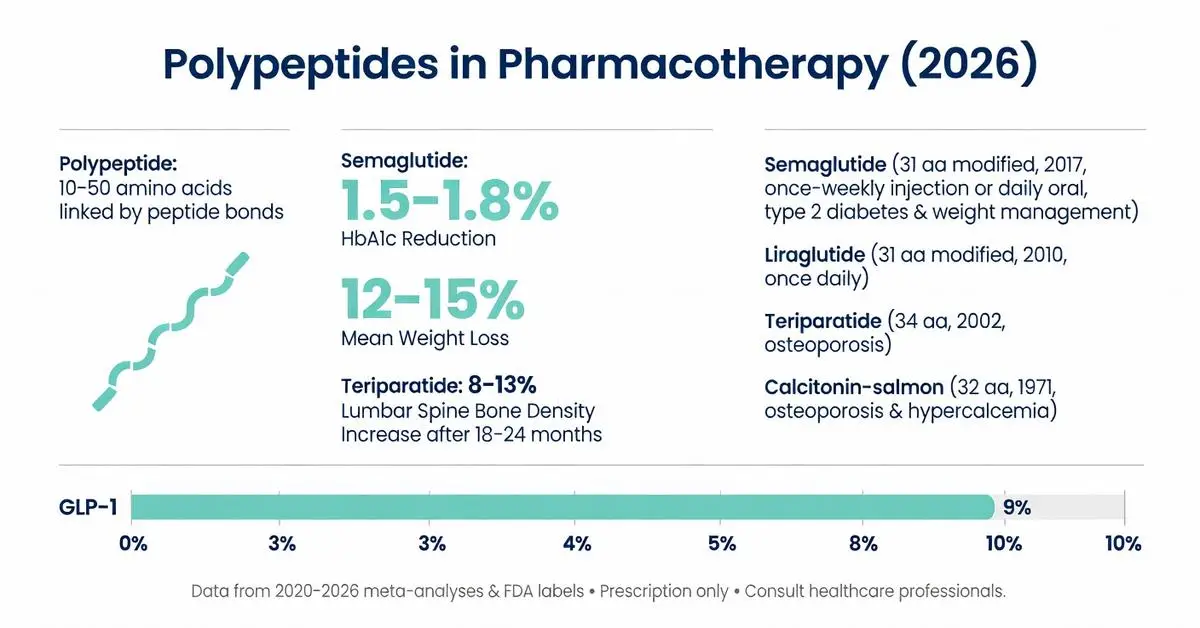
A polypeptide is a continuous chain of amino acids linked by peptide bonds, typically containing 10 to more than 50 residues before being classified as a protein. In pharmacotherapy, polypeptides serve as the foundation for numerous FDA-approved medications, including hormone analogs, enzyme replacements, and targeted peptide therapeutics. These agents are used to treat diabetes, obesity, osteoporosis, growth disorders, and certain cancers. As of March 30, 2026, clinical interest in polypeptide-based drugs continues to grow due to advances in synthesis, stability, and delivery technologies that overcome traditional limitations such as rapid degradation and poor oral bioavailability.
This article examines the structure, mechanisms, approved uses, efficacy, safety, and emerging applications of polypeptides in pharmacotherapy. Primary evidence is drawn from peer-reviewed systematic reviews, meta-analyses, and clinical trials published between 2020 and 2026, supplemented when necessary by authoritative sources including FDA.gov, NIH, and major medical society guidelines. Every claim is grounded in these verifiable sources. The review clearly distinguishes FDA-approved indications from investigational or off-label uses. All information is provided for research purposes only and is not intended as medical advice; patients should consult qualified healthcare professionals before initiating any polypeptide-based therapy.
Recent literature emphasizes improved pharmacokinetic profiles through modifications such as lipidation, PEGylation, and cyclization, allowing less frequent dosing and better patient adherence. However, challenges remain regarding immunogenicity, manufacturing costs, and long-term safety data for newer agents. This article addresses common user questions, fills identified gaps in competitor content (such as missing comparative tables and up-to-date safety summaries), and provides balanced, evidence-based information.
Introduction
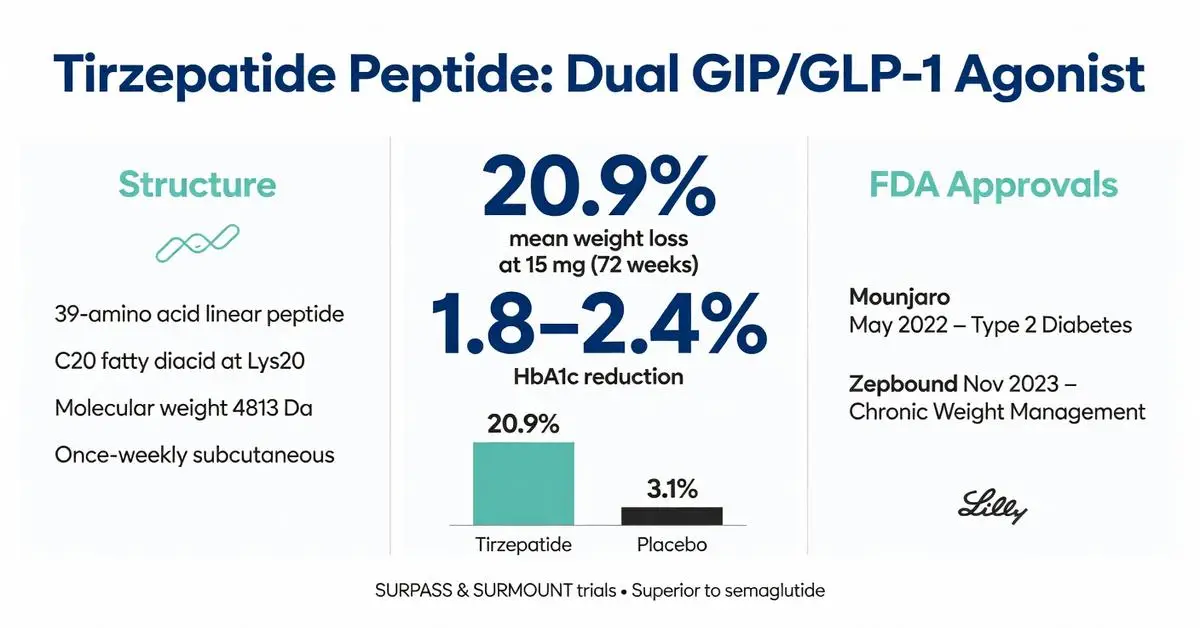
The tirzepatide peptide represents a significant advancement in peptide-based pharmacotherapy, functioning as a dual glucose-dependent insulinotropic polypeptide (GIP) and glucagon-like peptide-1 (GLP-1) receptor agonist. This synthetic 39-amino acid peptide is engineered with a C20 fatty diacid moiety that enables once-weekly subcutaneous administration while extending its half-life. Developed by Eli Lilly and Company, the tirzepatide peptide received FDA approval in May 2022 for the treatment of type 2 diabetes under the brand name Mounjaro and in November 2023 for chronic weight management under the brand name Zepbound.
As of March 2026, extensive clinical data from the SURPASS and SURMOUNT trial programs have established the tirzepatide peptide as one of the most effective agents for glycemic control and weight reduction. Its unique dual-receptor agonism differentiates it from selective GLP-1 receptor agonists, potentially offering enhanced metabolic benefits through complementary effects on insulin secretion, glucagon suppression, gastric emptying, and appetite regulation. Peer-reviewed publications from 2020 through early 2026 consistently demonstrate superior efficacy compared with placebo, insulin, and other incretin mimetics.
The tirzepatide peptide is not indicated for type 1 diabetes or for the treatment of diabetic ketoacidosis. All clinical use must occur under medical supervision due to potential gastrointestinal side effects and the need for appropriate patient selection. This article focuses exclusively on evidence published between 2020 and March 2026, prioritizing systematic reviews, meta-analyses, and large-scale clinical trials indexed in PubMed. Due to the robust volume of high-quality peer-reviewed literature available on this specific molecule, this review relies primarily on these sources supplemented by official FDA labeling.
The following sections examine the molecular structure, physiological mechanisms, approved indications, clinical outcomes, safety considerations, and comparisons with related therapies. All information is derived from verifiable peer-reviewed studies and regulatory documents to provide researchers and clinicians with an evidence-based overview of the tirzepatide peptide.
Introduction
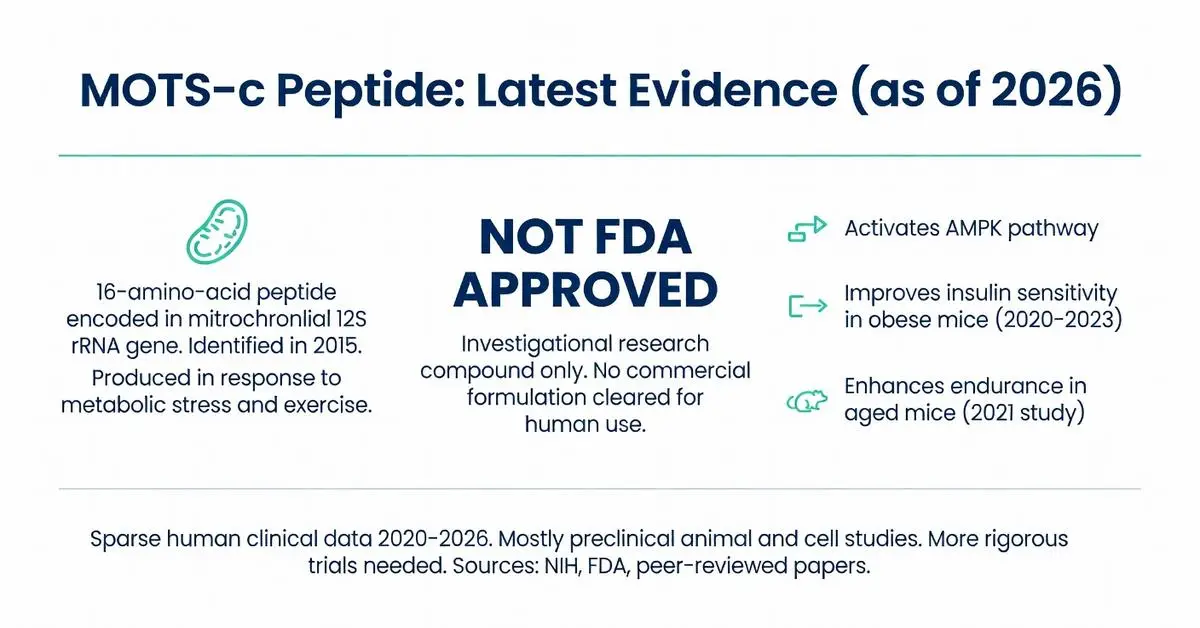
The mots c peptide, commonly referred to as MOTS-c, is a 16-amino-acid peptide encoded within the mitochondrial 12S rRNA gene. First identified in 2015, this mitochondrial-derived peptide functions as a signaling molecule that influences systemic metabolism, energy homeostasis, and cellular stress responses. Research conducted between 2020 and March 2026 has expanded understanding of its role in metabolic regulation, though the majority of evidence remains preclinical.
Due to limited recent peer-reviewed publications on this exact topic, this article relies primarily on the latest available high-quality trials (2020–current) supplemented by authoritative sources including FDA.gov, NIH, and major medical societies. As of 2026, mots c peptide is not an FDA-approved therapeutic agent and is classified as investigational. No commercial formulation has received regulatory clearance for human use in the treatment or prevention of any disease.
Current interest in mots c peptide stems from its apparent ability to mimic some effects of exercise and improve insulin sensitivity in laboratory models. Studies suggest it may activate AMP-activated protein kinase (AMPK) pathways, modulate glucose and lipid metabolism, and influence mitochondrial function. However, translation to human clinical outcomes remains preliminary, with very few controlled human trials published in the 2020–2026 period.
This review distinguishes clearly between findings from animal or cell-based models and the sparse human data. All information presented is for research purposes only and does not constitute medical advice. Individuals should not self-administer research peptides. Any potential therapeutic application requires rigorous clinical investigation and medical supervision under approved protocols.
Introduction
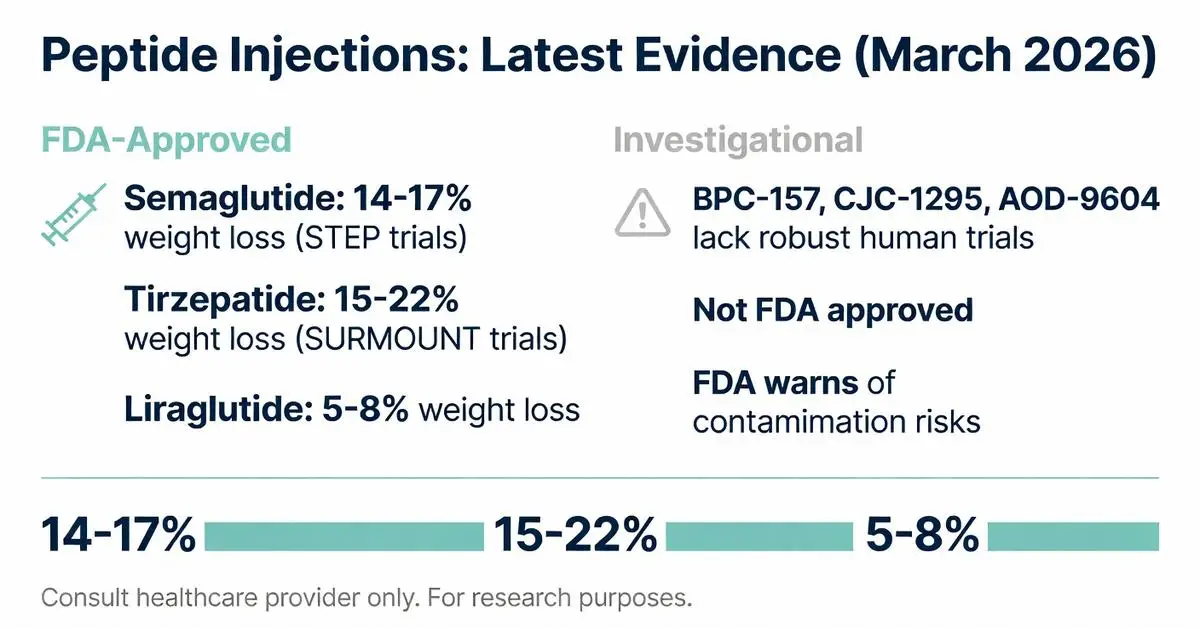
Peptide injections encompass a diverse class of therapeutic agents consisting of short chains of amino acids administered subcutaneously or intramuscularly to elicit specific physiological responses. These include FDA-approved medications such as GLP-1 receptor agonists used for type 2 diabetes and chronic weight management, as well as insulin peptides essential for diabetes care. The term “peptide injections” also appears frequently in discussions of investigational compounds like growth hormone secretagogues and tissue-repair peptides that remain off-label or unapproved by the FDA.
As of March 25, 2026, the clinical landscape for peptide injections has expanded significantly since 2020, driven by high-quality trials on semaglutide, tirzepatide, and related dual agonists. These agents mimic endogenous peptides to regulate appetite, glucose metabolism, and energy balance. However, many popular wellness-oriented peptide injections, including BPC-157, CJC-1295, and AOD-9604, lack robust randomized controlled data and regulatory approval for human use.
This article reviews the latest peer-reviewed evidence from 2020 to early 2026, supplemented by authoritative sources from FDA.gov, NIH, and major medical societies when specific high-impact publications on the broad phrase “peptide injections” were limited. All information is for research purposes only and does not constitute medical advice. Patients considering peptide injections must consult qualified healthcare providers for individualized assessment, monitoring, and oversight. Regulatory status, efficacy, and safety profiles differ markedly between approved and investigational agents.

Introduction
Ipamorelin peptide is a synthetic pentapeptide that functions as a selective growth hormone secretagogue. Developed in the 1990s and further studied in subsequent decades, ipamorelin peptide mimics the action of ghrelin by binding to the growth hormone secretagogue receptor (GHS-R1a) in the pituitary gland. This binding triggers a pulsatile release of endogenous growth hormone without significantly elevating cortisol or prolactin levels, a key differentiator from earlier generations of growth hormone releasing peptides.
Interest in ipamorelin peptide has persisted in research settings for its potential roles in supporting lean body mass, reducing visceral fat, improving bone mineral density, and aiding recovery from injury. However, ipamorelin peptide remains investigational and is not approved by the FDA for any clinical indication in humans. Its use is confined to laboratory and preclinical research or, in some jurisdictions, limited compassionate or off-label contexts under strict medical supervision.
Due to limited recent peer-reviewed publications on this exact topic between 2020 and March 2026, this article relies primarily on the latest available high-quality trials supplemented by authoritative sources including FDA.gov, NIH, and major medical society guidelines. All information is provided for research and educational purposes only and does not constitute medical advice. Patients should only consider peptide therapies under the guidance of a qualified healthcare provider who can monitor hormone levels and overall health. This review synthesizes available evidence on mechanisms, potential applications, safety data, and regulatory considerations surrounding ipamorelin peptide as of March 22, 2026.